
Blog

Subscribe to receive our free Beginner's Guide to Psychedelic Integration.

Can Psychedelics Reveal Truth, or Just Change Your Mind?
When someone has a profound psychedelic experience and emerges with strong convictions about the nature of reality, what should they do with those convictions? A therapist on philosopher Chris Letheby's careful argument that psychedelic experiences can produce genuine insight — particularly into the constructed nature of the self — without requiring the metaphysical claims that often accompany them.
There's a particular kind of conversation that happens in the weeks and months after a powerful psychedelic experience.
The person who has had the experience returns from it changed. They've seen something. Felt something. Understood something. They want to talk about it, and as they try, they find themselves making claims that sound, in ordinary daylight, somewhere between profound and embarrassing. I understood the nature of reality. I encountered God. I saw that everything is connected. I learned that death isn't real. I knew, for those hours, exactly what the universe is.
Even a sympathetic listener often doesn't know what to do with these reports. The experience clearly mattered. The person clearly isn't lying. Something happened that they're trying to convey. But the claims being made about reality itself often go further than what any experience, however powerful, could actually justify.
This is one of the most important questions in psychedelic medicine, and it's underaddressed in most popular conversation about the field. When someone emerges from a profound psychedelic experience with strong convictions about the nature of reality, convictions they didn't have before and that feel utterly certain, what should they do with them? Are they genuine insights into something deeper? Or are they powerful experiences the brain is producing for its own reasons, with no special access to truth?
The philosopher Chris Letheby has written one of the most important books on exactly this question. Philosophy of Psychedelics, published by Oxford University Press in 2021, takes the philosophical questions about these experiences as seriously as the clinical and neurological ones. His answer is more interesting than the usual debate allows, and I think it's clinically essential for anyone considering or integrating psychedelic experiences.
The Question the Book Is Actually Asking
It's easy to assume Letheby is looking for middle ground between two camps.
On one side sits the mystical view, which treats psychedelic experiences as windows onto deeper reality. Ego dissolution reveals the true nature of the self. Mystical experiences are encounters with something genuinely transcendent. The medicine opens doors ordinary consciousness keeps closed. This view has deep roots in Indigenous traditions, in 1960s thinkers like Aldous Huxley, and in much contemporary spiritual psychedelic culture. It honors the felt depth of these experiences.
On the other sits a blunt reductionism, which treats them as brain events. Powerful, sometimes useful, ultimately just neurochemistry. The sense of cosmic significance is a side effect of altered brain function. The mystical content isn't real. This view honors scientific caution, and in its cruder forms it dismisses what people have actually experienced as somewhere between delusion and chemistry.
But Letheby isn't splitting the difference. He's a naturalist, and the book is a defense of naturalism, the view that the natural world is all there is. His argument is that naturalism has been sold short. You do not have to abandon it to take these experiences seriously, because the therapeutic and epistemic benefits of psychedelics don't actually depend on any exotic metaphysics being true.
That's a stronger and more interesting claim than a compromise position. He's saying the reductionist was right about the metaphysics and wrong about what follows from it. You can take these experiences seriously without taking them literally.
The Comforting Delusion Objection
The book's central target is what Letheby calls the Comforting Delusion Objection.
It's the worry that psychedelic therapy might work only by deluding people with false metaphysical beliefs. That the depression lifts because the person now believes the universe loves them, or that they've encountered God, or that death isn't real. If that's the mechanism, the objection goes, then the therapy is working through deception, and that's ethically problematic even if it relieves suffering.
The objection deserves to be taken seriously. If psychedelic therapy primarily produced relief by installing false beliefs, the therapist would be implicated in a kind of psychological con. A well-meaning, helpful con, but one whose mechanism depends on deceiving the patient.
Letheby's response is methodical. He argues that the therapeutic benefit doesn't depend on metaphysical conclusions at all. It depends on something else: a change in the sense of self, and specifically a direct experience of the self's constructed nature.
This is the key move. Let me unpack it.
What's Actually Being Revealed
When someone experiences ego dissolution, when the felt sense of being a separate, continuous self temporarily loosens, they're not necessarily discovering anything about the metaphysical structure of the universe. They're discovering something quite specific about themselves. The self they ordinarily experience as solid and continuous is something constructed. Something the brain is doing. Something more flexible and less essential than it feels.
This is not a metaphysical claim. It's a claim about your own mind. And it's almost certainly true. The neuroscience converges with the phenomenology: the self is a model the brain builds, not a fixed entity it contains. Letheby's own account is more specific still. He describes the ordinary sense of self as held together by predictive self-binding, and psychedelics as temporarily unbinding it. That unbinding is what the default mode network research has been circling for years.
People who experience this directly, even briefly, often emerge with a different relationship to themselves. Less identified with the suffering self. More aware that the patterns they've been running aren't permanent features of who they are. More able to consider that change is possible at a deeper level than they had imagined.
Philosophers call this knowledge by acquaintance, a distinction that goes back to Bertrand Russell. It's knowing something not as an abstract claim but through direct experience. A person who has never been heartbroken can know intellectually that heartbreak is painful. A person who has been heartbroken knows it differently. Letheby argues that psychedelic experience can produce knowledge of the constructed self in this richer, directly known sense.
This kind of knowledge is real, valuable, and naturalistically respectable. You don't need to commit to any controversial metaphysical claim to acknowledge that someone who has directly experienced the constructed nature of their own self has learned something genuine.
What's Not Necessarily Revealed
The trouble comes when this insight gets extrapolated.
Many psychedelic experiences arrive with a sense of cosmic significance. The person doesn't just feel that their self is constructed. They feel they have understood the universe. Reality is consciousness. Everything is one. There is no death. We are all connected at the deepest level. I have encountered the divine.
These claims may be true. Some may be true in ways philosophy is slow to acknowledge. But they go further than the experience can justify. The experience produced certainty. The certainty is real. But certainty is not accuracy, and the very neurochemistry that produces the felt sense of profound insight may also produce overconfidence in conclusions that haven't been tested.
This is one of the genuine risks of psychedelic experience that doesn't get talked about enough. The medicines don't just produce experiences. They produce conviction. The conviction can outpace the justification. People can emerge holding metaphysical beliefs with the certainty of having known them directly, and build their lives around those beliefs in ways that don't always serve them.
I see this clinically. The person whose marriage breaks up because they've decided, after a ceremony, that their partner doesn't share their cosmic understanding. The person who quits a career they were good at to follow a calling they received during a journey. Sometimes these decisions turn out to be wise. Often, in retrospect, they look like someone acting on certainty that hadn't been tested against ordinary life. It's a version of a pattern I've written about elsewhere, where insight alone doesn't produce change and can even substitute for it.
The risk isn't that people have spiritual experiences. It's that they conflate the depth of an experience with the truth of every claim that emerges from it.
Letheby's Resolution
Letheby's framework offers a way through.
The therapeutic and epistemic value of psychedelic experience, on his account, doesn't depend on the metaphysical claims being true. It depends on something more modest and more defensible. The experiences alter the sense of self, expand what the person takes to be psychologically possible, and create conditions in which rigid patterns of thought and feeling can soften.
That is what produces lasting change. Not the conviction that consciousness is fundamental to the universe, or that one has encountered God. The experiential recognition that the self you've been suffering inside is not as solid as it felt. That recognition, even briefly held, can be liberating in ways careful philosophical argument never quite is.
For the metaphysical content, Letheby offers a concept worth borrowing: epistemic innocence. A belief or experience can be epistemically innocent when it delivers real epistemic benefits that couldn't be obtained any other way, even if the belief itself isn't justified. This gives you a way to hold the mystical content without either dismissing it or endorsing it. Something happened. It did real work. Whether its literal content is true is a separate question, and one you don't have to answer to benefit.
The practical stance that follows is something like: something real happened that I don't fully understand. I'll let it work on me without committing too quickly to what it means.
This is, I think, the most clinically and philosophically responsible way to hold psychedelic experience. It honors the depth without ceding judgment. It accepts the value without endorsing every claim.
Why This Matters for Integration
This question is not abstract. It comes up constantly in integration work with people who have had powerful psychedelic experiences.
The person who returns from a journey convinced of something they hadn't believed before faces a real choice. They can integrate the experience, letting its depth and meaning continue to work on them, without yet committing to particular metaphysical conclusions. Or they can quickly translate the experience into beliefs and start rearranging their life around them.
The first path tends to produce more sustainable change. The depth gets honored. The harder work of letting it gradually reshape ordinary life can unfold over months and years. The metaphysical questions stay open, examined against further experience and ordinary judgment.
The second path is vulnerable to a particular trap. Beliefs adopted in the wake of profound experience are sometimes adopted to protect the experience, to preserve its meaning by codifying it. But codification can become rigid. The person becomes someone with a particular spiritual identity, a particular metaphysical commitment, a particular way of seeing the world they're now invested in defending. The original openness that made the experience meaningful hardens into something more brittle.
This is one form of what's sometimes called spiritual bypass, using spiritual conclusions to avoid harder psychological work. The person who has decided that everything happens for a reason may use that belief to avoid grieving real losses, to bypass difficult feelings, to skip the slow work of actually changing how they live. The metaphysical conclusion gets installed where the harder work should be happening.
Good integration work helps people stay with the experience without rushing into beliefs that might not serve them. What was true about what you experienced? What's worth letting work on you? What conclusions are you reaching that may have outrun the evidence? These are questions a thoughtful integration therapist can help someone sit with, without dismissing what was real and without endorsing whatever the experience seemed to claim. It's closely related to how we make meaning of what we experience, which is its own skill and its own risk.
A Deeper Continuity
What I find most valuable about Letheby's framework is that it connects psychedelic experience to a question that applies far beyond psychedelics.
The same question shows up in religious experience. Mystical states in meditation. Encounters with grief, beauty, or terror that feel revelatory. Moments when ordinary reality seems to peel back and reveal something underneath. People throughout history have had experiences that produced powerful conviction about the nature of things, and how to hold those convictions has been a perennial problem.
The traditional contemplative answer, in many wisdom traditions, has been go slowly. Hold the experience without rushing to conclusions. Let it work on you. See what remains after months and years. The teacher's job, in many traditions, is partly to keep the student from getting attached to particular experiences or convictions, to keep the inquiry open rather than closing it with premature certainty.
Letheby is applying something like this wisdom to the modern question. The experiences are real. They may produce genuine insight, particularly into the constructed nature of the self. They also produce conviction that can outpace evidence. The careful work is holding the depth and the humility at once.
It's also worth saying that Letheby doesn't stop at damage control. The last substantive chapter of the book is about naturalizing spirituality, and he argues that genuine spiritual growth is available on a naturalistic picture. Spirituality, on his account, is largely a matter of unselfing. That's a claim with real teeth. It suggests the contemplative traditions were tracking something true about human minds even where their metaphysics may not survive scrutiny.
A Closing Thought
What's available in a careful psychedelic experience, on Letheby's view, isn't access to ultimate reality. It's something more modest and more useful. A direct, embodied recognition that you are not what you thought you were. That the self you've been suffering inside is one of many configurations your mind could take. That the patterns you assumed were essential to who you are are, in fact, optional.
This is real knowledge. It isn't metaphysical certainty about the universe, but it doesn't need to be. It's enough to support meaningful psychological change. It's enough to open doors ordinary consciousness keeps closed. It's enough, often, to make people's lives meaningfully better.
What it asks in return is a kind of intellectual humility. The willingness to hold what you've experienced without immediately codifying it. The capacity to let an experience continue to work on you without rushing to install conclusions. The patience to let depth become wisdom over time rather than mistaking the felt force of an experience for the truth of every claim that emerges from it.
This may be the most important integration skill there is. And it applies whether you've ever taken a psychedelic substance or not.
If you'd like to explore what careful, clinically informed integration of psychedelic experiences could look like, or to think through how to hold profound experiences of any kind without losing yourself in them, you're welcome to book a consultation.
Psychedelics: From Breakthrough to Backlash to Reckoning
The story of psychedelic medicine is often told as a heroic return after fifty years of unjust suppression — but the honest history includes both real promise and real problems, including the 2024 FDA rejection of MDMA-assisted therapy after serious ethical violations surfaced. A therapist on the full history, the current reckoning, and what responsible psychedelic care actually requires.
The story of psychedelic medicine is often told as a heroic one.
In the telling, scientists in the 1950s discovered remarkable therapeutic potential in compounds like LSD, MDMA, and psilocybin. They published hundreds of papers, treated thousands of patients, and were on the verge of transforming psychiatry. Then came the 1960s: countercultural excess, public backlash, and finally the 1970 Controlled Substances Act, which classified most psychedelics as Schedule I and effectively ended the research.
For fifty years, the story goes, this powerful family of medicines sat unused while millions suffered with conditions they might have helped. Now, thanks to a small group of dedicated researchers and a new generation of clinical trials, psychedelics are finally returning to medicine, and not a moment too soon given the depth of the contemporary mental health crisis.
This narrative is largely true. It's also incomplete. And the parts it leaves out matter.
I want to walk through the actual history of psychedelic medicine: the early promise, the legitimate concerns, the long suppression, the renaissance, and the very real reckoning the field is currently going through. The work Path of the Pearl is positioned around is bringing psychedelic-assisted therapy carefully into legitimate clinical practice. That depends on being honest about both what these medicines can offer and what's gone wrong, even recently, when they've been used without sufficient care.
The Forgotten Era of Scientific Optimism
The history before the 1970 shutdown is genuinely remarkable.
After Albert Hofmann's accidental discovery of LSD's psychoactive effects in 1943, psychedelics quickly became serious research tools. Through the 1950s and into the 1960s, mainstream universities, hospitals, and pharmaceutical companies investigated their potential. Studies were funded by reputable institutions. Findings were published in respected journals. By some estimates, more than 1,000 papers were published and tens of thousands of patients received psychedelic-assisted treatment during this era. This is the period Aldous Huxley was writing from, and the one Michael Pollan later went back to recover.
The early findings were striking, especially for conditions that had been resistant to other treatments. Alcoholism. Severe depression. Anxiety. Trauma. End-of-life distress. Some of the research foreshadowed exactly what later studies have rediscovered: that under the right conditions, psychedelic experiences could produce lasting psychological changes that ordinary treatment had not achieved.
It would be wrong to romanticize this era. The standards of clinical research were less rigorous than they are today. Many studies lacked proper controls. Informed consent was not what it is now. The line between researcher and patient was sometimes blurred. Some of what was called therapy would not pass ethical review today.
But the scientific interest was genuine, and the early signal was real. The compounds were doing something that seemed to matter.
What Actually Went Wrong
The collapse of psychedelic research wasn't driven entirely by politics, though politics was a major factor. The fuller story involves several converging problems.
Excesses outside the lab. Psychedelic use expanded rapidly beyond clinical and research settings in the 1960s. Recreational use grew. Some users had genuinely harmful experiences. Cases of prolonged psychosis, suicide, and psychiatric hospitalization made the news. The medicines that had been used carefully in supervised settings began to be used carelessly in entirely different ones, and the predictable harms followed.
Loss of institutional control. Figures like Timothy Leary moved beyond research and into advocacy, encouraging widespread use. Whatever Leary's other merits, his approach undermined the scientific case. The medicines came to be associated with countercultural rebellion rather than with rigorous medicine.
Genuine policy concerns. Some of the regulatory caution wasn't only political. The early research period had produced cases of harm that hadn't been adequately addressed. The infrastructure for safe administration outside clinical settings didn't exist. Even responsible researchers had concerns about how widely use was spreading and what the consequences might be.
Political opportunism. The Nixon administration's response was clearly political. The 1970 Controlled Substances Act placed all classical psychedelics in Schedule I, the most restrictive category, with no recognized medical use and severe limitations on research. This designation was disproportionate to the evidence and has been widely criticized since. But it didn't emerge from nothing. It emerged from a combination of real concerns and political calculation.
The consequence was decades of effective research silence. Studies didn't completely stop, but the regulatory and funding barriers made them extraordinarily difficult. Most academic researchers moved to other topics. The compounds remained in clinical memory primarily as something to be cautious about, and the careful clinical work of the previous era was largely lost.
The Cost of the Silence
It's worth pausing on what this silence cost.
For fifty years, while psychedelics sat unused, mental health conditions worsened in many populations. PTSD became increasingly recognized but remained difficult to treat. Treatment-resistant depression affected millions, with limited options after standard medications failed. Addiction continued to devastate communities. Suicide rates rose. Overdose deaths reached crisis levels. Anxiety and depression became, by some measures, the defining mental health challenges of the era.
Meanwhile, pharmaceutical innovation in psychiatry slowed dramatically. The major pharmaceutical companies, frustrated by the high failure rate of psychiatric drug development, scaled back their psychiatric programs. The treatments available in 2020 looked largely similar to the treatments available in 1990, and the people they didn't help remained without options.
Whether or not psychedelics would have closed this gap is impossible to know. The early research, while promising, was not rigorous enough to justify confident claims. But the absence of serious investigation during fifty years of growing mental health crisis represents, at minimum, a missed opportunity to find out.
This is part of what drove the renewed interest beginning in the late 1990s and accelerating through the 2010s. A new generation of researchers, often working at academic institutions like Johns Hopkins, NYU, and Imperial College London, began carefully picking up the work that had been abandoned. The early results were striking. Studies on psilocybin for treatment-resistant depression, end-of-life anxiety, and addiction produced effect sizes that conventional treatments rarely matched.
The psychedelic renaissance was underway.
The Renaissance and Its Cracks
For most of the 2010s, the story was straightforwardly hopeful.
Clinical trials were producing impressive results. The FDA granted Breakthrough Therapy designation to MDMA-assisted therapy for PTSD in 2017 and to psilocybin for treatment-resistant depression in 2018. Major academic centers established psychedelic research programs. Investment poured in. Oregon and Colorado moved forward with state-level legalization of psilocybin therapy. The field appeared to be on a steady trajectory toward FDA approval and mainstream integration.
Then, in August 2024, the FDA rejected MDMA-assisted therapy for PTSD.
The rejection was a shock to many in the field. The clinical trials, on their face, had shown impressive results. The need for new PTSD treatments was unquestionable. The expectation, both inside and outside the field, was approval.
The reasons were sobering. They tell a story the field is still grappling with, and one that anyone considering psychedelic-assisted therapy deserves to know.
Functional unblinding. MDMA produces effects so distinctive that participants and therapists could almost always tell whether they had received the drug or a placebo. This undermines the basic logic of the placebo-controlled trial. Expectancy effects became difficult to separate from pharmacological ones.
Selection bias. Many participants had used MDMA before and entered the trials expecting benefit. High rates of prior use combined with high prescreening failure rates suggested a population unlikely to produce regulatory-grade efficacy data.
Standardization problems. The psychotherapy component wasn't standardized in a way that would allow it to be reliably reproduced. The treatment manual incorporated elements from more than a dozen psychotherapeutic approaches, which made it difficult to know what exactly would be approved. I've written separately about why this problem is harder than it looks, and why the regulatory system was never designed to evaluate a drug delivered inside a relationship.
Safety characterization. The agency's review concluded that the sponsor had not adequately characterized the drug's safety profile, acute effects, duration of impairment, or abuse potential. Psychedelic Alpha's coverage of the complete response letter walks through the agency's specific requests, including a recommendation that the sponsor consider an independent third-party audit of all study records.
Ethical violations. Most seriously, allegations of therapist sexual misconduct at a Phase 2 trial site in Canada led to the retraction of three peer-reviewed papers in August 2024. The journal cited protocol violations amounting to unethical conduct. The person accused of assaulting a participant during her MDMA session was an unlicensed therapist working alongside a licensed co-therapist. An ICER review concluded that sexual boundaries were severely crossed with at least one patient in a Phase 2 trial. The participant's case has been the subject of extensive reporting and a podcast investigation.
These are not minor concerns. The patient who was harmed had come into the trial seeking help for PTSD. She left having been assaulted while in an altered state. The institutional response has been the subject of significant criticism, including allegations of inadequate transparency and a culture that allowed boundary violations to go unaddressed.
This isn't the entire field. But it points to real problems the broader psychedelic medicine movement has had to reckon with.
What This Has Taught the Field
The MDMA rejection forced an honest reckoning.
Boundary violations during altered states are uniquely dangerous. Patients under psychedelics are particularly vulnerable. Their judgment is altered, their defenses are softened, their capacity to refuse or report is compromised. Therapist sexual contact is always a serious violation. With patients in psychedelic states it is profoundly so. That the person involved in the Canadian case was unlicensed is not incidental. It points directly at how thin the training and credentialing infrastructure was, and in places still is.
The therapy component needs to be standardized. If a treatment involves both medicine and psychotherapy, the psychotherapy has to be defined clearly enough that what's being tested can be reliably reproduced. Treatments built around proprietary, multi-approach, hard-to-replicate frameworks pose real regulatory and ethical problems.
Adverse events must be reported. Underreporting of difficult experiences and adverse outcomes has been a real problem, whether out of misplaced enthusiasm, self-interested protection of the research, or simply inadequate procedures. The field is now building better infrastructure for honest reporting.
Functional unblinding is a structural problem. When a drug's effects are obviously different from a placebo, the placebo-controlled model breaks down. The field is exploring alternative designs, including active placebos and dose-finding approaches, but no full solution has emerged.
Advocacy and science don't mix well. MAPS was both a research organization and an advocacy organization with deep emotional investment in MDMA's approval. The conflict between these roles appears, in retrospect, to have compromised the integrity of the research in ways that were difficult to see from inside.
The relationship is part of the treatment, which makes it part of the risk.Two nervous systems in a room together are doing real work on each other. That's the mechanism these medicines depend on, and it's also why a poorly trained or poorly supervised practitioner is dangerous in a way that has no equivalent in ordinary pharmacology.
Where Things Stand Now
Three things have happened since I first wrote about this, and together they've changed the picture considerably.
The FDA published final guidance. In July 2026, the agency released Psychedelic Drugs: Considerations for Clinical Investigations, finalizing a draft first issued in June 2023. It addresses trial design, safety characterization, therapist-delivered interventions, and long-term follow-up. These are precisely the areas the MDMA rejection turned on. For the first time, developers have a written standard rather than an inference drawn from a rejection letter.
The MDMA application came back. In August 2026, the company now called Resilient Pharmaceuticals, formerly Lykos Therapeutics and before that the MAPS Public Benefit Corporation, resubmitted its NDA for MDMA-assisted therapy. Notably, it did so without running the additional Phase 3 trial the 2024 rejection called for, arguing that the core efficacy and safety data remained sound. Whether the FDA agrees is an open question, and a consequential one.
Psilocybin moved closer. Compass Pathways reported positive results from its first Phase 3 trial, COMP005, in June 2025, and from the second, COMP006, in February 2026. In July 2026 the company released 26-week durability data from COMP006. A rolling New Drug Application is underway with initial FDA review in progress, and final submission is expected in the fourth quarter of 2026. The company anticipates launch in the first half of 2027, contingent on both FDA approval and DEA rescheduling. That second step is easy to overlook and it isn't automatic.
If you want the trial details rather than the regulatory timeline, I've written a closer look at the Compass psilocybin data.
What This Means for Where We Are
The honest picture is complicated.
The clinical promise remains real. Studies continue to show that psychedelic-assisted therapy can reach conditions like treatment-resistant depression, end-of-life anxiety, and certain addictions that other treatments have not. The neuroscience has advanced significantly, and there are now coherent biological models of why these compounds work the way they do.
At the same time, the field is in a real moment of reckoning. The MDMA rejection was not simply a regulatory setback. It surfaced genuine problems about ethics, study design, institutional culture, and how to integrate medicine and psychotherapy responsibly. Some were always present. Some grew as the field expanded into territory it wasn't quite ready for.
State-level legalization adds another layer. Oregon's Measure 109 and Colorado's Proposition 122 opened legal psilocybin therapy in those states ahead of federal approval. These programs have produced both genuine help for patients and real concerns about quality control, training standards, and oversight. The infrastructure for safe psilocybin therapy outside the federal framework is still being built.
Outside the clinic and state programs, an ecosystem of retreats, ceremonies, and underground guides continues to operate. Some of this work is careful and helpful. Some is reckless. Some has caused serious harm. The current legal limbo doesn't make this work disappear. It just makes it harder to regulate.
For anyone considering psychedelic-assisted therapy, this means the choice is more complicated than it sometimes appears. Legal access is limited. The quality of available care varies enormously. The field is still figuring itself out. And the marketing, whether from retreat centers, ketamine clinics, or some psychedelic therapists, sometimes overstates what's known.
What Path of the Pearl Stands For
I want to be honest about where this practice sits in the larger picture.
I support careful, responsible development of psychedelic-assisted therapy. I believe the early clinical research and the deeper neuroscience point toward something real. I'm watching the Compass pipeline with cautious hope, and preparing for what legal psilocybin therapy will require if and when it becomes available in California.
I also believe the field has serious work to do. The MDMA rejection was not unjust. The ethical violations that surfaced are not isolated incidents to be dismissed. The standards for therapist training, boundary management, informed consent, adverse event reporting, and research integrity need to be substantially higher than they have been. Patients deserve protection precisely because the medicines are powerful and the states they produce are uniquely vulnerable.
What I try to offer is what I think the field most needs. Serious depth-oriented psychotherapy as the foundation. Careful clinical use of the legal psychedelic medicines, currently ketamine, as one tool among many. Rigorous attention to preparation and integration. Honesty about both the potential and the limits. That set of commitments is close to what I'd call the four pillars of responsible psychedelic care. When psilocybin therapy becomes legally available, I plan to continue this work with the same approach.
What I don't want to be is a participant in the next wave of psychedelic enthusiasm that gets out ahead of what we actually know how to do well. The history above is a cautionary tale. The field that gets this right will be slower, more careful, and more honest than the one that's been moving most loudly through the last decade.
A Closing Thought
The story of psychedelics is not a simple morality tale of suppression and return. It's a more complicated story about powerful compounds, human institutions, the difficulty of doing good research on subjective experience, and the ways enthusiasm and caution have both, at different times, failed to serve patients.
What's clear is that something real is being studied. Under the right conditions, with the right preparation, in the right relationship, with proper integration, these medicines can help people whose suffering has not yielded to other treatments. What's also clear is that the right conditions is harder to achieve than the field has sometimes acknowledged, and that getting it wrong has real costs to real people.
For anyone considering psychedelic-assisted therapy now or in the future, the most important questions aren't about whether the medicines work. They work, for some people, in some conditions, under the right circumstances. The important questions are about the circumstances. Who is providing the care. What their training and supervision look like. How they handle preparation, the experience itself, and integration. How they think about boundaries, ethics, and harm. Whether they're honest about what they don't know.
The history of this field offers both promise and warning. Both deserve to be heard.
If you'd like to discuss what careful, responsible work in this space could look like for you, you're welcome to book a consultation.
When Two Nervous Systems Meet: The Science of Co-Regulation in Healing
When two people are in close attuned interaction, their nervous systems begin to coordinate at the neural level — and recent psychotherapy research shows that this inter-brain synchrony actually increases over the course of effective treatment and correlates with symptom reduction. A therapist on what the science of co-regulation reveals about how healing happens, why the therapeutic relationship may be one of the most powerful clinical mechanisms we have, and what this means for psychedelic-assisted work.
There's a moment, in good therapy, that's hard to describe but unmistakable when it happens.
The room quiets. The client came in activated, heart racing, mind looping, body braced. Then they begin to soften. Their breathing deepens. Their shoulders lower a fraction. Their voice slows. Nothing has been said that would explain the shift. The therapist hasn't offered a clever interpretation or a particularly skillful intervention. Something else has happened.
What's happened, increasingly, can be measured.
A growing body of neuroscience research is showing something remarkable. The technique is called hyperscanning, and it records the brain activity of two people simultaneously. When two people are in close attuned interaction, their nervous systems begin to coordinate. Brain rhythms align. Heart rates can synchronize. Breath patterns drift toward one another. The two separate biological systems remain distinct, but they begin to function as a coupled system. Researchers call this inter-brain synchrony.
This isn't woo. The studies use EEG, fMRI, and functional near-infrared spectroscopy (fNIRS), all established methods of measuring brain activity. The synchrony is real, measurable, and increasingly understood to be one of the important biological mechanisms underlying human connection.
I want to walk through what this means, because it changes how we understand what therapy actually does. It also illuminates something important about why relationship sits at the heart of healing, in psychedelic work and in everything else.
What Co-Regulation Actually Is
You experienced this before you had language for it.
Infants don't regulate themselves. Their nervous systems are far too immature. The capacity to settle from distress, to find calm after activation, to digest food, to sleep, to feel safe: none of this is something infants do alone. They borrow it from the regulated nervous systems of the adults around them.
When a baby is upset and a caregiver picks them up, holds them close, breathes slowly, hums quietly, speaks gently, something specific is happening. The caregiver's nervous system is doing the regulatory work that the baby's system can't yet do for itself. The baby's heart rate slows toward the caregiver's. The baby's breathing matches the caregiver's rhythm. The baby's stress chemistry quiets as the caregiver's calm chemistry transmits, through touch and sound and presence, into the baby's system.
This process, called co-regulation, was foundational to your developing nervous system. Every time you were soothed as a child, you weren't just being comforted in some psychological sense. Your physiology was being literally regulated by another body. Over thousands of these interactions, your nervous system slowly built the capacity to do some of this work on its own. That capacity is what eventually becomes self-regulation in adulthood.
But here's what's important to understand: co-regulation never stops mattering. It doesn't get replaced by self-regulation. Adults regulate each other constantly. A partner's calm presence at the end of a hard day. A friend's steady listening when you're falling apart. A therapist's grounded presence when you're working with difficult material. The presence of a beloved animal. The steady voice of a parent on the phone. All of these are doing the same biological work that the caregiver did for the infant. Your nervous system finds its way back to baseline by borrowing regulation from another nervous system.
This isn't poetic. It's literal. And the research is starting to show us how it works at the neural level.
What the Hyperscanning Studies Are Revealing
When two people interact, their brains don't operate independently. Recent research is mapping how closely they actually coordinate.
A 2025 systematic review of 30 hyperscanning studies found that inter-brain synchrony is generally reduced in anxiety, depression, and autism, particularly in prefrontal and temporoparietal regions involved in social cognition. Stress was more complicated. Depending on context, it drove synchrony both up and down. The authors are careful to say the evidence is not yet strong enough to treat synchrony as a clinical biomarker, and that most conditions have only a handful of studies behind them.
Still, the direction is striking. The struggles with connection that so often characterize psychological suffering aren't only psychological. They appear to show up at the level of inter-brain coordination itself. The disconnection people feel may not live only in their experience. It may live in their physiology.
Other research has looked at what strengthens this coupling.
A 2023 study by Ellingsen and colleagues found that during clinical interactions involving pain, clinicians' prefrontal activity dynamically synchronized with patients' somatosensory responses. The strength of that neural concordance correlated with how strong the patient rated the therapeutic alliance. In other words: how much the clinician's brain was actually attuned to the patient tracked with whether the patient felt they had a real therapeutic relationship.
A small hyperscanning study on breath found that when two people focused on their own breathing while coordinating a simple physical task together, EEG coherence increased in frontal and central regions. Fifteen dyads, and the authors urge caution about how far to generalize. But it points at something worth paying attention to: shared interoceptive attention, feeling your own breath in the presence of another person feeling theirs, may strengthen the neural coupling between you.
Inter-brain synchrony has been observed in cooperative tasks, conversation, parent-child interaction, music-making, and everyday close relationships. The more attuned and coordinated the interaction, the more the brains involved appear to align.
This is, I think, the beginning of empirical confirmation for something therapists, parents, and lovers have always known intuitively. Something real happens between people when they're truly together. The hyperscanning research is starting to show us what that something is at the neural level.
What This Means for Therapy
In 2025, researchers reported something that caught my attention. In psychotherapy, inter-brain synchrony between patient and therapist increased over the course of treatment, and that increase correlated with symptom reduction.
Two things are worth saying about this study before we go further.
It's a proof of concept. The sample was small and the treatment focused on test anxiety, so this is a demonstration that the measurement is possible and promising, not an established finding about therapy in general.
And there's a result that complicates the story. The rising synchrony correlated with reduced symptoms and better session quality, but it did not correlate with a stronger therapeutic alliance. That's not what you'd predict if synchrony were simply a readout of how good the relationship feels. It may be measuring something the alliance questionnaires don't capture. Or the alliance measures may be catching something synchrony doesn't. Either way, the neat version of this story isn't the version the data supports yet.
With those caveats in place, the finding still challenges a particular assumption about what therapy is doing. The dominant cultural model treats therapy as primarily about content: the insights, the techniques, the cognitive reframing, the processing of memories. The relationship between client and therapist is often framed as a context in which the real work happens.
The research increasingly suggests the relationship itself may be one of the mechanisms. Not the context for the work, but a substantial part of the work. The slow, gradual coupling of two nervous systems over time, in steady weekly sessions, may be doing as much therapeutic work as anything explicit being said.
This makes sense in light of how human nervous systems develop. They learned to regulate through relationship. They continue to need relationship in order to update. When old patterns are stuck, particularly the patterns laid down in early caregiving relationships, they often can't be reached through cognitive work alone. This is part of why insight by itself so rarely creates change. Those patterns were laid down in the body, in interaction with another body. They tend to need to be reached the same way.
A therapist's calm, attuned, dependable presence, week after week and year after year, is not just supportive. It may be doing direct neurobiological work on the patient's nervous system. The patient borrows regulation, repeatedly, until something starts to update. The brain that had been organized around chronic dysregulation begins to organize around something else.
This is, in many ways, what depth therapy has always understood but lacked language for. Relational analysts have written for decades about the alliance as curative rather than merely enabling. Stephen Porges, with his polyvagal theory, reframed it as the activation of the social engagement system through co-regulation. Allan Schore and Bonnie Badenoch have written about right-brain-to-right-brain attunement as a primary healing process. The hyperscanning research is beginning to show, with neural data, what these clinicians have been describing all along.
Why This Matters for Psychedelic Therapy
This research has particular implications for the kind of work Path of the Pearl is oriented toward.
In conventional psychotherapy, the relationship matters but the medicine isn't part of the picture. In psychedelic-assisted therapy, the medicine is doing significant work, and the relationship between client and therapist arguably matters more rather than less.
Here's why. During psychedelic experiences, the nervous system is in a particularly open and vulnerable state. The usual defenses are softened. Material that ordinarily stays guarded can surface. The client is, in some sense, more available to receive what's around them than they normally would be.
This means that whoever is in the room with them has unusual influence on what happens. Whoever's nervous system is in proximity. Whoever's tone and presence and breath rhythm is filling the space. A therapist who is themselves regulated, attuned, present, and skilled can co-regulate the client through experiences that might otherwise be overwhelming. A therapist who is anxious, distracted, or poorly trained can fail to provide the regulation the client needs, sometimes with lasting consequences.
This is part of why the field has emphasized so consistently that the medicine alone is not the treatment. The medicine and the relationship together are the treatment. And what the relationship provides isn't only insight or interpretation. It's nervous-system support during a vulnerable state, co-regulation in the moments when the client most needs another nervous system to borrow from.
It's also, uncomfortably, one of the hardest parts of the field to standardize. The FDA's rejection of MDMA-assisted therapy turned in part on exactly this problem. If the relationship is part of the treatment, how do you specify it, measure it, and hold it to a standard? The regulatory system has no good answer yet. Thoughtful Indigenous traditions and contemporary integration practitioners have long treated the healer's role as more than technical. The research is now suggesting it may also be biological. They are part of the medicine
What This Means for Healing More Broadly
If co-regulation through relationship is one of the primary mechanisms of psychological healing, it changes how we should think about a great deal.
It means that isolation is itself injurious, not just emotionally but biologically. People who lack consistent attuned relationships in their lives are not just lonely. Their nervous systems are missing a kind of regulation they evolved to require. Chronic loneliness has well-documented effects on cardiovascular health, immune function, cognition, and mental health. Whether missed co-regulation is the mechanism is a reasonable hypothesis rather than a settled finding, but it's the one that fits the rest of the picture.
It means that community matters in a particular way. Not just for connection's sake, but as a source of nervous-system support that supplements what any individual can do alone. Cultures that prioritize extended family, communal living, and regular shared rhythms build co-regulation into the structure of daily life. Cultures that prioritize individual autonomy often build it out.
It means that therapy is more powerful than we usually credit, and also more demanding. The presence and attunement of the therapist isn't just useful. It may be doing direct biological work. Good therapy requires therapists whose own nervous systems are sufficiently regulated to do this work without depleting themselves. This is one of the reasons therapists need their own support: supervision, personal therapy, sustainable caseloads, time off.
It means that animals may regulate us too. Dog owners and equine therapists have said so for years, and the research on animal-assisted work is developing, though it's earlier and more mixed than the popular version suggests. The proposed mechanism is the same one: co-regulation between two nervous systems, with the human's stress patterns gradually entraining toward the animal's calm.
And it means that what we offer each other matters more than we often realize. The friend who sits quietly with you while you cry. The partner who breathes slowly when you're spiraling. The colleague who stays grounded while everyone else panics. These aren't just nice gestures. They are nervous-system support, co-regulation in action. We are constantly regulating each other, or failing to, whether we're aware of it or not.
A Practical Note on What This Looks Like
If co-regulation is real and measurable, what helps us actually access it?
A few things the research and clinical experience point toward.
Slow breath, especially shared breath. Breathing slowly in the presence of another person whose breathing is also slow, through meditation, intentional practice, or simply sitting together quietly, appears to engage co-regulation. The hyperscanning evidence here is preliminary, so treat this as a promising direction rather than a proven one.
Eye contact, when it's safe. Sustained, attuned eye contact, not staring and not analyzing, engages social engagement circuits powerfully. For many people, particularly those with trauma histories, this needs to be approached carefully. Eye contact can also activate threat systems if the original experience of being looked at was unsafe. But when it works, it's deeply regulating.
Voice tone. The voice is one of the strongest co-regulatory channels we have. A warm, low, slow voice supports parasympathetic activation. Polyvagal theory specifically identifies the voice as one of the primary tools of social co-regulation. Therapists, parents, and lovers know this implicitly, but it's worth being conscious of how you use your voice with people you care about.
Touch, when it's wanted and consensual. Physical contact between safe people is one of the most powerful regulatory mechanisms available. Holding hands. A hand on the shoulder. A hug. The presence of a hand on the back during difficulty.
Steady, embodied presence. Sometimes the most regulating thing a person can do for another is simply be in the room, settled, breathing, available. Not problem-solving. Not advising. Not even talking much. The presence itself is medicine.
These aren't techniques in the manipulative sense. They're ways of inviting your own nervous system into a state that can offer co-regulation to another. They work best when they emerge naturally from genuine care, not from script.
A Closing Reflection
What I find most moving about this body of research is what it confirms about something so often dismissed.
For much of modern psychological thinking, the inner life has been treated as primarily individual. Your mind, your suffering, your healing. Other people show up as factors in your environment, but not really as part of who you are.
The co-regulation research is challenging this picture. It suggests we are not the separate, self-contained selves we've been taught to be. We are nervous systems shaped by other nervous systems, regulating against and through each other, more interdependent than the cultural story has acknowledged. It's the same boundary that softens in other contexts too, between self and other, and between self and world.
This is sometimes framed as a loss of independence. I think it's the opposite. It means that healing is available in ways we hadn't fully understood. It means that the people in your life are not just nice to have. The steady presences. The attuned therapist. The calm friend. The regulated animal. Even the rare encounter with a stranger whose presence somehow settles you. They are part of how you continue to become well.
And it means that you, in turn, are part of how others become well. The presence you bring into the rooms you enter is doing work, whether you know it or not. The regulated nervous system is medicine for everyone around it. The dysregulated one transmits, too.
For people sitting with chronic patterns of suffering, this is hopeful information. You are not alone with your nervous system, even though it can feel that way. There are pathways through other nervous systems back toward the regulation your system has been seeking. Some of those pathways are professional. Some are personal. Some are communal. Some, increasingly, can involve careful work with psychedelic medicines held by skilled practitioners. But they share an underlying mechanism: two nervous systems meeting, attuning, and slowly teaching each other something neither could learn alone.
If you'd like a place to explore what this kind of relational work could look like for you, you're welcome to book a consultation.
From Ego to Eco: How Psychedelics Change Our Connection to Nature
Psychedelic experiences can produce a lasting, measurable increase in how connected people feel to the natural world. Some studies track the shift for two years. Here's what the research shows about ego dissolution, setting, and why this matters for anyone living with the quiet disconnection of modern life.
One of the most consistent findings in psychedelic research is also one of the strangest. It's the one I think gets the least attention in popular conversation.
People who have profound psychedelic experiences often emerge with a lasting, measurable change in how connected they feel to the natural world.
Not as a metaphor. Not as a fleeting mystical impression that fades within days. As a stable shift, measurable on psychological scales, persisting in some cases for two years or longer after the experience.
A growing body of research, much of it out of Robin Carhart-Harris's group at Imperial College London, has been documenting this. The landmark study by Hannes Kettner, Sam Gandy and colleagues, From Egoism to Ecoism, found that people who took psychedelic substances showed significant increases in nature relatedness, a well-validated psychological measure of how connected someone feels to the natural world. The researchers measured that increase at two weeks, at four weeks, and again at two years.
What predicts this shift? Two things, primarily. The first is the depth of ego dissolution during the experience, the temporary loosening of the felt sense of being a separate self. The second is the environmental setting of the experience itself. Sessions that happen in nature produce stronger and more lasting increases in nature connectedness than those that happen indoors.
This finding is more important than it first appears. It connects to questions about psychological healing, ecological crisis, and what it actually means to be a self. I want to walk through it carefully, because I think it's one of the more meaningful discoveries to come out of the psychedelic research renaissance.
What Nature Relatedness Actually Is
The concept of nature relatedness sounds like it might be soft, a self-report of whether you like trees. The actual psychological construct is more specific and more clinically meaningful.
Nature relatedness measures how much a person experiences themselves as part of the natural world rather than separate from it. It includes felt sense, identity, and lived experience. Someone with low nature relatedness might appreciate nature aesthetically but experience themselves as distinct from it. Nature is over there, I am over here. Someone with high nature relatedness experiences themselves as embedded in, continuous with, and intrinsically connected to the natural world. The trees aren't just outside. They're somehow part of the same fabric the person is part of.
This isn't a personality quirk. A meta-analysis of the research has linked nature relatedness to higher subjective well-being across a wide range of studies. The broader literature associates it with lower rates of anxiety and depression, greater meaning in life, higher levels of positive emotion, reduced stress, improved cognitive function, and greater pro-environmental behavior.
In other words, the felt sense of being connected to nature isn't just nice. It appears to be one of the underrecognized pathways to psychological health.
That makes the psychedelic finding clinically significant. In the Kettner data, increases in nature relatedness moved together with increases in psychological well-being. It suggests that part of what's healing about psychedelic experience isn't only the loosening of rigid patterns or the processing of difficult material. It may also be the restoration of a connection most people in modern life have lost.
What Ego Dissolution Has to Do With It
The mechanism the research keeps pointing to is ego dissolution.
Ego dissolution is the experience, during certain psychedelic states, of the felt sense of being a separate self becoming less solid. The boundaries between you and the world soften. The narrative of who you are quiets. The constant background processing that ordinarily produces the experience of being yourself, here, distinct from everything else, temporarily releases its grip.
This experience can be unsettling, especially for people who haven't been prepared for it. But for many people, particularly when held in supportive conditions, it's described as one of the most meaningful experiences of their lives. The walls that have always seemed to separate them from the world thin. What's left isn't nothing. It's a kind of expanded, more spacious sense of belonging. The philosopher Chris Letheby has written carefully about what this kind of self-loss actually involves, and why it doesn't require abandoning a scientific view of the mind.
What the research is showing is that this experience of dissolved selfhood doesn't just produce a passing impression. It produces a lasting recalibration of how connected the person feels to everything outside themselves. The wall, once it's been seen as a wall rather than as reality, doesn't quite go back up the same way.
For many people, this shows up most palpably as nature connectedness. They emerge from the experience and find that they notice trees differently. They feel an unfamiliar tenderness for animals. They recognize themselves as part of the living world in a way that had previously been intellectual rather than felt. The shift is often subtle but persistent.
It also shows up as social connectedness, and the research is increasingly clear about this. People who experience ego dissolution often report lasting increases in their felt sense of connection to other people. They describe more empathy, more openness, more willingness to be moved by other people's experiences. The boundary that dissolved wasn't just between self and nature. It was between self and other, more broadly.
A 2025 review paper in Current Opinion in Psychology proposes that what psychedelics may produce is a generalized self-other overlap. A softening of the boundary that ordinarily separates the self from everything else, with implications for connection to nature, to other people, and to life as a whole.
Why This Matters in This Moment
I want to spend some time here, because the finding intersects with something I see often in my practice, and something I think more therapists need to be naming.
Many of my clients are quietly suffering from forms of distress that don't have neat clinical names. A vague but persistent sense of disconnection from themselves, from others, from the world. A grief they can't quite articulate about the state of nature, the loss of biodiversity, the climate news that arrives daily. A loneliness that goes deeper than relationships, into something more existential.
The term eco-anxiety has begun to enter clinical conversation, though it's still underdeveloped. What I see in clients includes that and goes beyond it. It's a particular kind of suffering that comes from living inside the contemporary version of human selfhood. Separated from the rest of the living world. Individuated to the point of isolation. Identified with a self that's measured by achievement and consumption rather than belonging.
This isn't the same as depression in any standard diagnostic sense. The eco-philosopher Joanna Macy named the outer version of it the Great Unraveling, the ongoing fraying of ecological and social systems. What I'm describing is the inner correlate of that unraveling, the version that shows up in a therapy room. People feel it. Most don't have language for it. And the cultural script tells them to keep going, keep working, keep consuming, keep producing, even as something inside them knows that the disconnection is itself a kind of wound.
What the psychedelic research is suggesting is that this disconnection isn't permanent. The felt sense of being separate from the natural world is not a fixed feature of being human. It's a construction, culturally and neurologically and developmentally, and constructions can change.
Indigenous traditions have known this forever. Many contemplative traditions have known it. Now the research is describing it in neurological terms. For people who are quietly suffering from the modern condition of disconnection, and for anyone asking what psychedelic experience has to do with meaning, this is a meaningful piece of information.
Why Setting Matters So Much
The Kettner study and several that have followed found something specific about where the experience takes place.
People who had psychedelic experiences in natural settings showed larger and more lasting increases in nature relatedness than those who had experiences indoors. The medicine and the environment worked together. Neither alone produced the same effect.
This makes sense in light of how psychedelics work. The medicine softens the predictive scaffolding that ordinarily structures experience. What replaces that scaffolding, temporarily, is whatever the person is actually encountering. If the encounter is with trees, sky, water, the texture of soil, the rhythm of wind, the surrounding life of a forest or shoreline, then the new experience that consolidates has those elements woven through it.
If the encounter is with a clinical room, fluorescent lights, and a screen, the experience integrates around those.
This isn't a judgment about clinical settings. They have important uses, particularly for people whose suffering requires the safety and structure of a controlled environment. But it's a reminder that set and setting aren't soft variables in psychedelic work. They shape what gets built during the experience and what consolidates afterward.
For traditions that have used these medicines ceremonially for thousands of years, this isn't news. Many Indigenous psychedelic traditions take place in or near specific natural settings, often connected to sacred land, with the natural world understood as part of the medicine itself. The research is now describing, in neurological language, something traditional practitioners have long known.
What This Tells Us About Healing
This research changes how I think about psychedelic-assisted therapy, and about therapeutic work more broadly.
For a long time, clinical psychology has framed mental health primarily as an internal matter. Fix the thoughts. Process the trauma. Regulate the nervous system. Build healthier internal structures.
These are real and important. But the research on nature relatedness suggests something additional. Part of what's actually wrong in many forms of psychological suffering is relational in a deeper sense than therapy ordinarily considers. Not just our relationships with other people, though those matter. Our relationship with the living world we're embedded in.
When that relationship is severed, and modern life severs it in countless small ways, people don't always know how to name what's missing. They feel disconnected, anxious, depressed, restless. The conventional categories don't quite capture what's actually happening. They've lost something fundamental about being a living creature among other living creatures, and the loss is so culturally normalized that it goes unnamed.
What psychedelic experiences can offer, in this view, isn't only an opening into difficult inner material. They can also offer a temporary restoration of a connection that's been culturally suppressed. The experience of being part of the living world rather than separate from it. The recognition that the boundary between self and nature, while useful for some purposes, isn't fundamental.
When this connection is felt directly, something can change that no amount of cognitive understanding alone produces. People come back from these experiences and their lives often look different. Not because they've solved anything in particular, but because they've remembered something about being alive that they had forgotten. What they do with that afterward, in the weeks and months of integration, is where the change either takes root or fades.
How This Can Show Up Without a Medicine
I want to be careful not to suggest that psychedelics are the only path to this kind of shift. They aren't. The research keeps pointing back to the underlying mechanism, the softening of the boundary between self and world, and that mechanism can be reached through many pathways.
Time in nature, especially time spent slowly and attentively, increases nature relatedness even without any medicine. A daily walk in a natural setting, with attention turned outward, gradually shifts the felt sense of self over weeks and months. Not dramatically, but real.
Contemplative practice produces similar shifts. Sustained meditation, particularly practices oriented toward non-dual awareness, also softens the boundary between self and world. People who've practiced for years sometimes describe a quality of belonging much like what psychedelic experiences can produce more rapidly.
Deep relational experiences can do this too. Extended time with another being whose presence quiets the usual narrative of separation. People often describe this in the company of certain animals, with elders or wise teachers, in caregiving relationships, in long-term partnerships that have moved beyond the early relational dynamics into something more spacious.
Even ordinary moments can produce small versions of this shift. Sunset light. The texture of moss. A child sleeping. The sound of wind in trees. Many of us have felt, in such moments, a brief loosening of the sense of being a separate self, a quiet recognition that we belong to something larger.
The psychedelic experience can produce these states more reliably and more powerfully. But the shift it produces isn't qualitatively different from what's available, in subtler forms, in ordinary life. The medicines may amplify and accelerate a recognition that's always available to anyone willing to attend carefully.
A Closing Reflection
What I find most meaningful about this research isn't the clinical implications, though those matter. It's the philosophical implication.
The deep assumption of modern Western life is that we are separate selves, individuated and self-contained, distinct from the natural world and from each other. That assumption turns out to be one possible configuration of consciousness, not the only one. There are other ways to experience being alive. The walls can soften. The connection can be felt directly.
For people in psychological distress, particularly the modern forms that involve disconnection, isolation, and the felt absence of meaning, this is hopeful information. Whatever sense of separation has been organizing your suffering is not the final truth about who you are. It is one model your brain has been running. The model can soften.
For the larger questions of our moment, the ecological grief and climate distress and felt unraveling of the natural world we're all part of, this research offers something else. The disconnection many of us have been living inside is not just an individual problem. It's a cultural condition with individual consequences. But the connection that's been lost is not gone. It's recoverable.
This is, I think, part of why psychedelic therapy has felt so important to so many people in this moment. Not because the medicines are magic. Not because they fix anything in particular. But because they can help people remember something that the world we've built has obscured. That we belong to the living world. That we are not alone in it. That the wall between self and nature is more provisional than it seems.
If you'd like to explore this kind of work, through depth therapy, integration support, contemplative practice, or some combination, you're welcome to book a consultation. And whether or not psychedelic experience is part of your path, the recognition this research points toward is available, in quieter forms, to anyone willing to look for it.

What Is Internal Family Systems, and Why It Fits Psychedelic Work So Naturally
IFS says the mind isn't one voice with occasional conflicts. It's a system of parts, each with a job it took on for a reason, and a Self underneath that was never damaged. Why that model has become the most natural fit for psychedelic work, what Richard Schwartz noticed when colleagues started combining them, and what the evidence does and doesn't yet show.

There's a model of the mind that, once you start using it, becomes hard to see things any other way.
It's called Internal Family Systems, or IFS, developed by psychologist Richard Schwartz in the early 1980s. Schwartz started as a family therapist, working with the kinds of difficult dynamics that play out between people in households. He noticed, listening carefully to his patients, that they kept describing something similar happening inside themselves. Different voices. Different reactions. Parts of them that wanted different things, that argued, that took over, that hid.
He began asking his patients about these parts directly. What surprised him was that they could describe them in remarkable detail. Each part had a history, a role, a job it had taken on, a relationship to other parts. The internal world, he realized, looked surprisingly like the families he'd been working with. A system of distinct individuals, each with its own perspective, all trying to coexist.
Over decades, this observation became one of the most influential models in contemporary psychotherapy. A 2025 scoping review in Clinical Psychologist examined 27 peer-reviewed studies and called IFS a promising therapeutic approach, particularly for PTSD, depression, and chronic pain.
It's worth knowing what that rests on. Seventeen of those studies were case studies. Two were randomized controlled trials. The review's central point is that the evidence base needs to be considerably stronger, and it notes that the growing popularity of IFS may itself contribute to selective publication of positive results. Promising is the accurate word. It isn't the same as established, and I'd rather say so than oversell a model I find genuinely useful.
In recent years, IFS has also emerged as one of the most natural therapeutic frameworks for working with psychedelic experiences. Schwartz himself has co-authored a clinical manual on integrating the two.
I want to walk through what IFS actually is and why this pairing has become important, because for people considering psychedelic-assisted therapy, or sitting with their own difficult inner experience, the framework offers something genuinely useful.
The Mind as a System, Not a Monolith
Most of us were raised on a particular assumption about the mind: that there's one you inside, who has thoughts and feelings and makes decisions. When that you feels conflicted or confused, wanting one thing and doing another, knowing better and behaving worse, it's usually framed as a failure of integration, willpower, or self-knowledge.
IFS proposes something different. The mind isn't a single voice with occasional conflicts. It's a system of distinct parts, each with its own perspective, history, and concerns. What feels like confusion or self-contradiction is often just multiple parts active at once, with different agendas.
You've probably noticed this without naming it. A part of you wants to go to bed early; another part stays up reading. A part of you wants to leave a job; another part is afraid of the change. A part of you knows you should call your father; another part is still angry at him. Most of the time we treat these as opposing impulses inside a unified self. IFS treats them as distinct parts in genuine relationship with each other, each with its own legitimate concerns.
This isn't a fringe idea. Many therapeutic traditions have recognized something similar. What IFS contributes is a precise, workable model of how the system is organized.
The Three Kinds of Parts
In Schwartz's framework, the parts that make up the inner system fall into three broad categories.
Exiles. These are parts that carry pain, usually old pain, often originating in childhood. They hold the grief, fear, shame, or loneliness that the system couldn't fully process at the time. To protect the rest of the system from being overwhelmed, exiles are usually pushed out of awareness. They don't disappear. They're held away, often for decades.
Managers. These are parts that work to prevent the exiles from being triggered. They organize your life. They keep you productive, perfectionistic, controlled, alert. They run the inner critic that pushes you to do better, the overthinker that anticipates every threat, the high-functioning self who keeps everything moving. Their job is to make sure the wounded exiles stay safely contained, by managing the external world so carefully that the underlying pain never gets stirred up.
Firefighters. These are emergency responders. When the managers fail and exiled pain starts to surface, firefighters come in to extinguish the feeling fast and by any means necessary. They show up as explosive anger, substance use, dissociation, binge eating, compulsive scrolling, impulsive behavior. They're not trying to ruin your life. They're trying to stop you from feeling something the system has decided would be unbearable.
The key insight, and what makes IFS clinically powerful: none of these parts are bad. They're all trying to help, in the only way they know how. They've taken on extreme roles because the system needed them to. The work isn't to eliminate parts. It's to understand them, hear them, and gradually allow them to take on healthier roles.
The Self at the Center
Underneath the parts, IFS proposes, there is something else: the Self.
The Self is not a part. It's the core of who you are, and according to Schwartz it's present in everyone, including those with the most severe trauma histories. The Self has qualities that Schwartz organized into what he calls the eight Cs: curiosity, calm, clarity, compassion, confidence, courage, creativity, and connectedness.
When the Self is in the lead, when none of the protective parts are fully active, the system can rest. Parts can communicate. Old wounds can be approached with care rather than avoidance. The whole inner ecosystem becomes more flexible.
Most people, most of the time, are not in Self. They're blended with one part or another. Taken over by the manager who's running everything, fused with the anxious part, identified with the inner critic. The work of IFS therapy is helping the Self take leadership, so that parts can be in relationship with the Self rather than dominating the system.
This is harder than it sounds. Many people, when they first encounter IFS, can't easily access the Self at all. The protective parts have been in charge for so long, and so completely, that the Self has become hard to reach. Part of the slow work of IFS is precisely about uncovering the Self that's always been there, beneath the layers of protection.
How IFS Therapy Actually Works
In an IFS session, the work is direct and experiential. A therapist might invite you to notice a part of you that's been activated. The part might appear as a felt sense in the body, an image, a voice, an emotion. You're invited to turn toward it with curiosity rather than judgment.
What does this part want you to know? What's it been doing for you? How long has it been here? What's it afraid would happen if it stopped?
The part, surprisingly often, has clear answers. Once it feels seen and heard, it tends to soften. It may show you what it's been protecting, usually a younger, more vulnerable part holding old pain. The work then moves to that deeper layer. Meeting the exile, witnessing what it's been holding, allowing it to be released from the burden it took on.
This is called unburdening. When an exile is unburdened, the system reorganizes around it. The managers and firefighters that have been working so hard to contain it can relax. The whole inner family becomes more peaceful.
This sounds abstract. In practice it's deeply moving and often quite immediate. People who have done years of cognitive therapy without reaching a particular pattern can sometimes meet it directly through IFS in a single session. Not because the pattern was simple, but because IFS reaches it through a different door.
Why Psychedelics and IFS Fit Together So Well
Here's where the conversation gets clinically important.
Schwartz himself, in an interview with Psychedelics Today, described what he had observed when colleagues began bringing IFS into psychedelic-assisted therapy: "There are times where you just can't convince these protective parts to let us get to an exile and heal it. And a psychedelic session can expedite that pretty easily, it seems."
That's a striking observation from one of the most influential therapists of his generation. What he's describing is a specific clinical challenge in IFS work. The protective parts that won't budge, that won't let the Self approach what they're guarding. For some people these protectors have been in place so long, with such conviction, that ordinary therapy can't move them. The exiles stay walled off. The healing stalls.
Psychedelics, in current neuroscientific models, work in part by temporarily softening the brain's defensive structures. Walls that have been firm become permeable. Material kept carefully at a distance can come into view. From an IFS perspective, this means protective parts often relax during a psychedelic experience, sometimes dramatically, allowing direct contact with what they've been protecting.
What this looks like clinically: people in psychedelic states often report experiencing parts of themselves with unusual clarity. Different aspects of their psyche appear as distinct voices or images. The inner critic becomes visible as a separate figure rather than feeling like the truth. A frightened child part may show up palpably. The Self, with its curiosity and compassion, often becomes more accessible than usual.
Schwartz and his collaborators have argued that this convergence isn't coincidental. IFS and the psychedelic state share a structural compatibility.
Both emphasize multiplicity. IFS sees the mind as parts. Psychedelic experiences often present those parts vividly.
Both prize curiosity and compassion. The qualities IFS calls Self-energy are remarkably similar to what people often access during psychedelic experiences.
Both work experientially rather than cognitively. Neither relies primarily on insight or analysis. Both engage what's happening in the moment, in the body, in direct experience of inner material.
Both seek unburdening rather than suppression. Both frameworks aim to help wounded material be released rather than managed.
When practitioners trained in both bring them together, what emerges is a coherent approach that honors what the medicine opens and provides a framework for working with what arises.
What an IFS-Informed Psychedelic Session Looks Like
In practice, a psychedelic session integrated with IFS often unfolds something like this.
Preparation. Before the session, the therapist and client may begin meeting parts together. The client learns to recognize protective parts when they show up, to differentiate them from the Self, to approach inner experience with curiosity. This preparation matters. It gives the client a vocabulary and a way of relating to whatever emerges during the experience.
The session itself. During the medicine experience, the client may encounter parts in heightened form. The therapist's role is largely to support, hold space, and occasionally offer gentle guidance. What's that part wanting you to know? Can you ask it what it's protecting? The Self, more accessible than usual, can lead the work in real time. Material that protectors had been guarding can be met directly. Old burdens that exiles have been holding can begin to release.
Integration. This is where IFS becomes especially valuable. After the experience, much of the work involves continuing the relationships that opened during the session. The parts that became visible. The exiles that began to release their burdens. The Self that emerged. Integration isn't passive. It's the ongoing practice of staying in relationship with the inner system, supporting parts that are still adjusting to new roles, allowing the reorganization that began in the session to consolidate over time.
Without this framework, psychedelic insights often fade. The parts that briefly relaxed return to their old roles. The exile that almost unburdened pulls back behind the walls. With it, the changes that began in the session can be supported, stabilized, and woven into ordinary life.
What This Means for the Larger Conversation
The growing recognition of IFS as a natural partner to psychedelic therapy reflects a broader shift in how we think about healing.
For most of the 20th century, dominant therapeutic frameworks were cognitive. Fix the thoughts, change the behaviors, modify the beliefs. These work for some people, but they often don't reach the deeper layers where chronic patterns actually live.
IFS, alongside other depth approaches like somatic experiencing, AEDP, and contemporary psychoanalysis, represents a different orientation. Not fixing. Not eliminating. Understanding the system and helping it reorganize.
Psychedelic-assisted therapy, used carefully, can amplify what these approaches do. The medicine doesn't replace the work. It expands what's accessible to do the work on. The framework, IFS or another like it, provides the structure to make sense of what opens.
For people considering psychedelic therapy, this matters. The medicine alone, without a framework for working with what arises, can produce experiences that feel powerful but don't integrate. The framework alone, without the medicine, can produce gradual change that takes longer than some people have. Together they can offer something neither does well alone: an opening that becomes a reorganization.
A Closing Thought
What I find most beautiful about IFS, and about its convergence with psychedelic work, is the underlying premise. That beneath all of your protective patterns, beneath the wounded parts, beneath everything that has hurt you and everything you've done to protect yourself from being hurt, there is something undamaged. A core of curiosity, compassion, and presence that has been with you the whole time.
For people who have lived inside chronic suffering, this can be hard to believe. The Self can feel inaccessible, or even mythical. But it is, in the IFS view, always there. The work is not to create something new. It's to clear enough space for what's always been present to take leadership again.
Psychedelic experiences, when held well, can sometimes give people a direct encounter with this Self for the first time. Many describe it as the most meaningful experience of their lives. Not because something new appeared, but because they recognized something true that had been obscured.
The work afterward is letting that Self take a more permanent role in the inner system. Not all at once. Not without setbacks. But steadily, with practice and support, the parts that have been protecting and exiling can be welcomed home, and the Self that was always there can begin to lead.
When the Mind Stops Predicting
Contemplative traditions have said for millennia that something quieter sits beneath the self. A 2021 paper describes the same territory in the language of predictive processing, and proposes that insight works by subtraction rather than addition. What that means for meditation, for psychedelics, and for anyone carrying a self that has grown too heavy.
There's an old observation in contemplative traditions that goes something like this:
Beneath your thoughts, beneath your sense of being a separate self, beneath the constant narration of who you are and what's happening to you, there is something quieter. Something that's been there the whole time, that doesn't need any of the rest to exist.
For most of Western intellectual history, this observation was treated as poetry, or metaphysics, or the language of religious traditions that didn't quite translate into modern terms.
In the last decade, that's been changing.
A growing body of neuroscience research is showing that what contemplative traditions have been pointing at for thousands of years can be described, with surprising precision, in the language of modern cognitive science. What emerges from that research is useful to almost anyone, whether or not they ever sit on a meditation cushion.
In particular, a 2021 paper by Ruben Laukkonen and Heleen Slagter in Neuroscience and Biobehavioral Reviews, titled "From many to (n)one: Meditation and the plasticity of the predictive mind", offers one of the clearest scientific accounts I've seen of what meditation is actually doing to the brain. It lines up, beautifully, with what people who've practiced for a long time have always said it was doing. (The full text sits behind a publisher paywall for some readers. The PubMed record is open.)
I want to walk through it, because the implications reach well beyond meditation. They illuminate something about the work of healing, the relationship between contemplative practice and psychedelic experience, and what the deepest forms of psychological change actually require.
What Your Brain Is Always Doing
To understand what meditation undoes, it helps to start with what the brain is constantly doing in ordinary consciousness.
Recent neuroscience has converged on a picture of the brain as a prediction machine. Rather than passively receiving the world, your brain is actively generating predictions. About what you're seeing, what you're hearing, what your body is doing, what's about to happen, what kind of person you are, what other people think of you, what comes next.
These predictions operate at many levels and time scales.
Some are immediate and concrete. The prediction that the next sound from a familiar voice will be a familiar word. The prediction that your foot will meet the step you're about to take.
Some are more abstract. Predictions about how the day will unfold, how a relationship is going to feel, how you'll perform at the meeting tomorrow.
Some are very long-term. Predictions about who you are, what kind of person you've always been, what your life means, what you can and can't do.
The brain runs all of these constantly, mostly outside conscious awareness. The smooth flow of ordinary experience is largely the felt result of these predictions matching reality well enough that you don't notice them happening. You only become aware of the machinery when something goes wrong. When the step isn't where you expected. When someone responds in a way you didn't anticipate. When your sense of who you are gets challenged.
The deepest of these predictions, the ones running at the highest levels of abstraction over the longest time scales, are what produce the felt sense of being you. Your continuous identity. Your narrative self. The story of who you are.
What Meditation Actually Does
Here's where Laukkonen and Slagter's framework becomes interesting.
In their account, meditation works by progressively reducing these predictive processes. Not all at once, but in a particular order, from the most abstract and long-term predictions inward toward more immediate experience.
This happens across what they describe as a continuum of practice.
Focused attention, the earliest stage, works by stabilizing attention on a chosen object. The breath, a mantra, a sensation. This reduces distraction and quiets the most superficial layer of prediction, the constant low-level chatter about what's next.
Open monitoring, a more advanced practice, involves observing whatever arises in awareness without grasping or rejecting. This loosens the next layer, the automatic interpretive patterns that filter raw experience through learned categories. Thoughts still arise, but their hold weakens.
Non-dual awareness, the deepest form, works directly on the most fundamental predictive layer: the distinction between observer and observed, self and world. As this loosens, the felt sense of being a separate self can soften, sometimes dissolve entirely.
At each stage, the brain is doing less predicting and more experiencing. The layered architecture of self that generates ordinary consciousness becomes simpler, lighter, less insistent.
This is what the paper's title gestures toward. The many layers of selfhood gradually fall away. What remains is not nothing. It's experience itself, without the elaborate self-model that ordinarily organizes it.
This sounds esoteric. It's actually quite concrete in lived experience. Anyone who's had a moment of being fully present has briefly touched what the deeper meditative states reach more fully. Watching light through a window without naming it. Hearing music without thinking about anything else. Walking somewhere with no internal narration. The thinking-about-yourself layer quiets. What's actually here becomes more vivid. The sense of being a separate observer softens.
Insight as Subtraction, Not Addition
One of the most striking ideas in the paper concerns what insight actually is.
In ordinary thinking, we assume insight comes from adding something. New information, a new perspective, a new way of seeing the problem.
The paper proposes something different. Real insight often comes from removing something. The brain's models simplify. Unnecessary assumptions drop away. The complexity that had been obscuring something falls. What was always there becomes visible.
This is consistent with how meditators describe their deepest realizations. Not as the arrival of new content, but as the recognition of something already there, briefly seen clearly when the layers of model and narrative thinned enough to allow it.
The clinical implication I find moving is this. So much psychological suffering is the accumulation of models. Beliefs about who you are. Predictions about what's coming. Narratives about why things happened. Identities you've taken on. Stories you inherited. These accumulate over years until they start to feel like reality itself.
The work of healing, in this view, isn't always about adding healthier beliefs. Sometimes it's about gently dissolving the unhelpful ones. Letting the predictive machinery simplify. Letting the over-elaborated self-model lighten. Letting something more essential come back into view.
This is what people often report after sustained practice. Not new beliefs about themselves, but a thinning of the old ones. A spacious sense of being somehow more here and less defined.
Why This Matters Beyond Meditation
You might be reading this and thinking you're never going to become a serious meditator, so what does this have to do with you.
Here's what I'd offer.
The framework isn't really only about meditation. It's about the deeper principle that your sense of self, your patterns of suffering, and your predictions about the world are all constructions your brain is generating. Constructions can be modified.
This is hopeful in a way the medical model often isn't. You are not a fixed thing with permanent features. The depression you've lived with isn't written into your bones. The trauma patterns aren't a life sentence. The identity you've taken on isn't who you are. It's who your brain has been predicting you to be.
The predictions can change. The models can soften. The constructions can be revised.
This happens through many pathways. Meditation is one of the most direct. Psychotherapy is another, particularly the kinds that work at depth, with the body, in relationship. Psychedelic experiences are a third. Major life transitions, encounters with art or nature that move you, deep contemplative experiences in religious contexts. All of these can produce the kind of model-simplification the paper describes.
The path matters less than the underlying mechanism. What's needed is sustained experience that loosens the rigid models the suffering self has been running on, and lets something more essential reorganize.
Meditation and Psychedelics as Two Routes to the Same Place
This is where the paper opens onto something directly relevant to the work I care about.
If meditation works by gradually reducing the brain's predictive processes, softening the elaborate self-model and simplifying the layers of prediction, then it's doing slowly what psychedelics appear to do quickly.
Both can produce experiences of dissolved selfhood, expanded awareness, present-centered consciousness, and the recognition that the ordinary self is a construction rather than a fixed feature of reality. Both appear to reduce top-down predictive control. Both loosen the rigid scaffolding through which we ordinarily organize experience.
What differs is the path. Psychedelics produce the opening rapidly, through pharmacology. Meditation produces it gradually, through trained attention. One is dramatic and brief. The other is patient and cumulative. Each has gifts and limitations.
What's clarifying about seeing them through the same lens is the recognition that they aren't opposites. They're complementary routes into the same territory. People who do both, mindfully, often find that each reinforces the other. Meditation deepens what the medicine opens. The medicine reveals what meditation has been working toward.
Both, incidentally, tend to surface parts of the self that ordinary consciousness keeps organized and out of view.
I'd add one caution here, because it's where this framing can go wrong. The idea that both routes reach the same place is a claim about mechanism, not a claim that they're interchangeable. Practice builds capacity over years. A medicine session opens a window and then closes it. Treating one as a shortcut to the other misunderstands both.
What This Means for the Work
For people sitting with patterns of suffering, this framework offers something specific.
Your suffering is partly a problem of overly rigid models. Not just thoughts, but the deeper predictive scaffolding that generates the experience of being you. These accumulated over years, often originated in environments where they were adaptive, and have outlived their usefulness.
The work may involve simplifying models rather than adding more. I'd flag this next part as something I've observed rather than something the paper demonstrates. People who have done a great deal of therapy sometimes seem more burdened rather than less, having accumulated insights, frameworks, names for their patterns, and stories about their wounds without any of the underlying scaffolding actually simplifying.
Practices that reduce prediction help. Meditation. Somatic work that brings you out of narrative and into the body. Time in nature where conceptual thinking quiets. Art that interrupts the usual filters. Therapy that can hold not-knowing. All of these slowly thin the layers.
Psychedelic therapy may have a specific role. For models that have become particularly rigid, the medicine can produce a window in which deeper restructuring becomes possible. The work continues afterward, through the slow practice of integration that lets new openings consolidate.
The deepest change isn't fixing yourself. It's letting the self soften enough that something more essential comes back into view. That isn't loss of identity. It's the recovery of something that was always there, beneath the construction.
A Word About What This Isn't
I want to be careful about something, because I've seen this framework misunderstood.
The idea that the self is a construction doesn't mean the self isn't real, or doesn't matter, or should be transcended. You are not less you because your continuous identity is a high-level prediction. The construction is doing important work. It lets you function, plan, stay in relationships, hold a coherent life.
The point isn't to dismantle the self. The point is that it can be held more lightly. You don't have to be defined entirely by the scaffolding you've built. There's something underneath, more essential and more present, that can be reached when the layers thin.
For people in pain, that's liberating. The depression isn't who you are. It's a layer of prediction that has gotten stuck. The trauma response isn't you. It's a pattern your brain has been generating. The harsh inner voice isn't the truth about you. It's one of many models running in the system.
These can change. With practice, with support, with patience, the patterns loosen and simplify and sometimes dissolve.
A Closing Reflection
What I find most moving about this framework is how it brings together two domains that have long seemed separate.
Contemplative traditions have spent thousands of years describing this territory. The gradual loosening of identification with thought and self. The recovery of present-centered awareness. The sense of being more whole when one is less defined.
Modern neuroscience has recently begun describing the same territory in the language of predictive processing and Bayesian inference.
Neither account is complete alone. Together they offer something rare, a description of deep psychological change that honors both the wisdom of old traditions and the rigor of contemporary science.
What this tells me, clinically and personally, is that becoming more well is also, in some sense, becoming less defined. Less identified with the suffering self. Less captured by the models generating the pain. More present to what's actually here, beneath the layers.
This is the work good meditation does. It's the work depth therapy does when it goes deep enough. It's the work psychedelic experiences, well held, can open. And it's work anyone can begin in any moment, by being present to what's arising without needing to predict, narrate, or define it.
Why Your Brain Prefers Familiar Suffering to Unfamiliar Healing
Depression is hard to leave partly because you can no longer picture the person you'd be without it. A 2023 model from psychedelic neuroscience calls this canalization: patterns that begin as sensible adaptations and slowly narrow the range of selves you can reach. Why insight alone doesn't undo it, and what actually does.
Ask someone who has been depressed for a long time to describe who they'd be without the depression.
Most people can't do it. Not in any detail. They can name what they'd stop feeling. They struggle to say what they'd start feeling, or what they'd want, or how they'd spend a Tuesday. The unsuffering version of themselves isn't a person they can picture. It's an absence where a person would go.
I've come to think this is one of the more important facts about stuck patterns, and that it explains something that otherwise looks like a failure of will.
You can know exactly what's wrong. You can articulate the pattern, trace it to its origins, and describe what a better arrangement would look like in the abstract. And still not move. Not because you're weak or unmotivated or secretly attached to your suffering. Because the alternative isn't real to you yet, in the specific sense that your system has no working model of it.
There's a framework that makes sense of this, and it comes from the same research group behind much of the recent work on psychedelics and the brain.
What Canalization Means
In 2023, Robin Carhart-Harris, Karl Friston, and a dozen colleagues published a paper proposing a single underlying feature common to much of psychopathology. They call it canalization.
The word comes from the biologist Conrad Waddington, who pictured development as a ball rolling across a landscape of valleys. The deeper the valley, the more strongly the ball is channeled into it. Apply that image to mental life and the valleys become habitual states, the well-worn paths your system falls into.
Their argument is that what makes a pattern pathological isn't its content. It's its entrenchment. Specifically, its degree of influence and its resistance to revision when new contexts or new evidence arrive.
And here's the part I find most useful clinically. They describe canalization as usually beginning as an adaptive response to adversity, distress, or dysphoria. It made sense once. It becomes a problem when it grows too dominating of a person's future cognitive and behavioral state-space.
Read that phrase slowly, because it's the whole thing.
State-space means the range of states you can reach. Every self you could be, every way you could respond, every configuration available to you. Canalization doesn't just make one valley deep. It shrinks the map. Over time, the depressed self isn't one option among many. It becomes most of what's reachable.
Which is why the person can't describe who they'd be without it. That version isn't hidden. It's out of range.
The authors are careful about one thing, and I want to repeat it. Canalization isn't inherently bad. Consolidating well-trodden paths is how learning works at all. A person with no deep valleys would have no skills, no habits, no stable character. The question is never whether a system is canalized. It's whether the canalization has become too deep and too dominating for the life the person is now living.
This connects directly to the too much order end of the spectrum I've written about elsewhere. Canalization is what excessive order looks like when you zoom in on a single pattern.
Why Insight Doesn't Reach It
If the problem were missing information, insight would fix it. Learn the true thing, replace the false thing, feel better.
That isn't how it goes, and the canalization model explains why.
The trouble isn't that you hold a wrong belief. It's that the belief sits at the bottom of a deep valley, and the system keeps rolling back into it regardless of what you've understood. Knowing you're safe doesn't flatten the valley. Understanding where a pattern came from doesn't flatten it either. The predictions about who you are that organize your experience were built from years of input, and a paragraph of insight doesn't outweigh them.
This is also why contradicting evidence so often fails to register. When someone is kind to a person who expects unkindness, the kindness tends to get absorbed rather than counted. It was pity. They want something. They don't know me yet. The valley is deep enough that new information rolls back down into the existing shape.
There's a version of this I find worth naming plainly. A pattern that resists revision is doing what it was built to do. It got built because revision was once dangerous or expensive. Calling it self-sabotage misses that entirely.
The Part That Feels Like Going Backward
Something I've watched often enough to consider it ordinary: people can get shakier when life improves.
Anxiety arrives when a relationship becomes healthier. Discomfort shows up as the chronic weight starts lifting. Someone doing genuinely well finds themselves drawn back toward an old arrangement they had already left behind.
I want to be careful about how I explain this, because the tidy story is that the brain is seeking the familiar, and the honest answer is that I'm describing a clinical observation rather than a finding.
But the canalization picture makes it legible. Leaving a deep valley means spending time on unfamiliar ground where the system has no reliable model of what happens next. That's genuinely destabilizing, even when the direction of travel is good. The old pattern was painful and it was known. The new one is better and it is not yet mapped.
People often read that period as evidence they're failing. It's closer to the opposite. Feeling unmoored as things improve is roughly what you'd expect from a system leaving territory it knows.
What Actually Updates a Model
If entrenchment is the problem, then the work is whatever reduces entrenchment. In practice that seems to mean a few things.
Repetition over revelation. One contradicting experience gets absorbed. Many, over time, start to reshape the landscape. Safety has to be felt again and again before safety becomes predictable.
Relationships that don't behave as predicted. A steady therapeutic relationship, a partnership that doesn't repeat the original pattern, a friend who stays. These are hard to explain away precisely because they're sustained and embodied rather than argued.
Practices that loosen habitual prediction. Meditation is the most studied of these, and it works slowly and from the inside.
Tolerating the unmapped stretch. The period between the old model loosening and a new one forming is uncomfortable by nature. Support through that stretch is often what determines whether someone stays with the change or retreats to what they knew.
I'd call these clinically well-supported rather than proven by the canalization paper specifically. The paper describes the mechanism. What follows from it for practice is inference, mine and other people's.
Where Psychedelics Fit
The canalization model has a companion. The REBUS model, from the same authors, proposes that psychedelics reduce the confidence weighting on the brain's existing predictive models, which has the effect of flattening the landscape those models sit in.
Flatten the landscape and the ball stops rolling automatically into the same valley. Patterns that felt like facts can briefly be seen as patterns. Evidence that would normally be absorbed has a chance to land.
The authors themselves speculate that previously dominant attractors, including pathological ones formed in response to trauma-related uncertainty, may be relaxed in an enduring way after successful psychedelic therapy.
Note the hedging in that sentence. It's theirs, and it's appropriate. REBUS remains a proposal, and direct testing of its core claims is still early.
What the framework does clarify is why the medicine alone isn't the treatment. Flattening the landscape doesn't determine where the ball goes next. If nothing new happens during the window, the old valleys are still there when precision returns. The integration work is what puts something else on the map.
One narrowing worth making. The strongest trial evidence for psychedelic-assisted treatment of trauma specifically involves MDMA, which isn't a classic psychedelic and works through a different mechanism. For treatment-resistant depression the classic psychedelic evidence is stronger. I'd rather be precise about that than let the categories blur.
The Honest Part
There's something humbling in this framework and I don't want to smooth it over.
If the difficulty is structural, then healing isn't mainly a matter of understanding or trying harder. It's the slow business of building a model of a life you haven't lived yet, using experiences you have to actually have rather than merely consider.
For people who grew up in chaos, or survived something, or spent decades inside a particular shape of suffering, that can be the hardest work they ever do. Not from weakness. From the fact that they're working against a system that got good at keeping them safe by keeping the map small.
There's grief in it too, which surprises people. The old predictions organized a life. They were wrong and they were load-bearing. Letting them go is a real loss even when it's also a release.
A Closing Thought
The useful thing about canalization is that it reframes the question.
Not what's broken in me. What has narrowed, and how far, and what would widen it.
Valleys that deep took years to cut, usually for reasons that made sense at the time. They don't flatten because you've understood them. They flatten through repeated experience of something else, held long enough for the system to believe it.
Which brings it back to where I started. If you can't picture who you'd be without this, that isn't a failure of imagination. It's an accurate report on the size of the map right now.
Maps can be redrawn. Slowly, and usually not alone.
Why Healing Lives at the Edge of Order and Chaos
Depression is a system stuck in too much order. Psychosis is a system that has lost coherence. And anxiety, which feels like chaos from the inside, turns out to behave more like a groove. A look at the criticality framework, what it gets right about where different kinds of suffering sit, and why knowing your direction changes what will actually help.
There's a way of thinking about the mind that I find quietly transformative, and that maps onto clinical experience more accurately than most other frameworks.
It comes from complex systems theory, the study of how systems with many interacting parts behave. It applies to brains, ecosystems, weather, and the dynamics of any living thing. The central observation is this:
Living systems function best when they're balanced near the edge between order and chaos.
Too much order, and the system becomes rigid. It can't adapt. Nothing new happens. It repeats itself.
Too much chaos, and the system loses coherence. Nothing connects. Patterns can't form. Function breaks down.
But near the edge between them, at a state scientists call criticality, the system has both stability and flexibility. It can hold its form while still being responsive to new information. It can change without dissolving.
This idea has real implications when applied to the brain. Once you see it, a lot of what happens in depression, anxiety, trauma, and psychedelic therapy starts to make sense in a new way.
I want to walk through the framework, because it's one of the most useful ways I know to understand what healing actually requires in the kinds of suffering that don't respond to simpler interventions.
What the Brain Does at Criticality
Here's a detail that surprised me, and it's worth getting right at the start.
The healthy adult brain does not sit exactly at criticality. It sits just below it.
That's the argument Robin Carhart-Harris and colleagues make in the paper this framework comes from. Entropy (scientific measure of randomness, disorder, or uncertainty in a system) is suppressed in normal waking consciousness, so the brain operates slightly on the ordered side of the critical point. And that suppression is useful. It's what gives ordinary consciousness its constrained quality, along with reality-testing and self-awareness.
So the goal isn't maximum flexibility. A brain in perfect criticality would be less reliable, not more. Ordinary waking life depends on a certain amount of holding steady, on a model your brain is generating and mostly trusting.
What matters is the distance from that point. Drift too far toward order and the system locks. Drift too far toward disorder and it loses coherence. Health is a workable range, not a knife edge.
When the brain is in that range, conscious experience is at its richest. Perception is vivid. Thought is flexible. The mind can move between focused attention and free association, between holding ideas steady and letting them recombine.
When it drifts toward too much order, experience constricts. Patterns lock. The same thoughts circle. Possibility narrows.
When it drifts toward too much chaos, experience fragments. Coherence breaks down. The thread of self and meaning gets harder to hold.
Depression as Too Much Order
This framework has been particularly useful for understanding depression.
The paper proposes that mental states can be understood along a spectrum of entropy, meaning informational disorder, or in less technical terms, how locked-in versus how flexible the brain's activity patterns are.
At one end is excessive order. The brain is doing the same things in the same ways. Activity patterns are repetitive. The system has gotten stuck.
This describes, in striking detail, what depression feels like from the inside.
The same thoughts return. The inner narrative loops. The future looks like the past. Nothing new feels possible. Motivation, novelty, and hope all depend on the brain's capacity to generate fresh patterns, and in depression that capacity has constricted.
The authors propose that psychedelics may work by normalizing pathologically sub-critical styles of thought, of the kind seen in depression, OCD, and addiction, returning the brain to a more critical mode of operating.
I want to flag something about this source before going further. The entropic brain paper is classified as Hypothesis and Theory. It's a proposal built on neuroimaging findings, not a demonstration, and the authors close by naming the studies that would test it. It has been enormously influential and I find it clarifying. It isn't settled science, and anyone presenting it as such is getting ahead of the evidence.
Anxiety Is Not What I Expected
Here's where I had to correct myself.
I used to assume anxiety belonged on the chaos end. It feels chaotic. Racing thoughts, scattered attention, a system that won't settle.
But look at what anxiety actually does over time. The same worry, on repeat. The same catastrophic prediction, arriving in the same shape, resistant to contradicting evidence. That's not disorder. That's a groove.
The research points the same direction. The paper notes that default mode network connectivity correlates positively with both depressive rumination and trait neuroticism, and cites imaging work finding positive correlations between serotonin 2A receptor binding and trait neuroticism and pessimism, which it links to inflexible patterns of negative thought.
So chronic anxiety looks more like excessive order wearing a chaotic costume. The subjective experience is turbulent. The underlying pattern is rigid.
That reframe changes what you'd expect to help. If anxiety were fundamentally a disorder problem, the answer would be more structure and more containment. If it's fundamentally a rigidity problem, then containment alone may just make a tight system tighter, and what's needed is some capacity to generate a different prediction.
In practice most people need both, and I'll come back to that.
What Actually Sits at the Chaos End
The paper is specific about which states belong on the high-entropy side. It names REM sleep and early psychosis alongside the psychedelic state, and groups them as what it calls primary states.
Early psychosis is the clinically important one. When the brain's capacity to maintain coherent models of self and world breaks down, that's a coherence failure rather than a rigidity problem. More entropy is the last thing that system needs.
Acute overwhelm belongs here too, in the sense that a person in the middle of it has temporarily lost the ability to organize experience into manageable form.
I'd be careful about placing trauma wholesale on either end. Trauma responses often look like both at once. The system is rigid in its predictions about danger and chaotic in its regulation. Which end dominates varies by person, and honestly by day
Where Psychedelics Fit
Psychedelics, in this framework, increase the entropy of brain activity. They loosen rigid patterns and move the brain toward higher disorder and more openness to new configurations.
For someone whose suffering is fundamentally about too much order, meaning locked depression, rigid trauma patterns, or calcified self-narratives, that direction of movement is the point. The medicine softens the rigidity. A pattern stuck for years can briefly be seen as a pattern. The system can reorganize.
This is part of why, for treatment-resistant depression, psychedelics can produce changes other treatments haven't reached. Traditional treatments often work within the existing patterns. Psychedelics work on the patterns themselves.
The durability question has some evidence behind it. In a Johns Hopkins follow-up study of 27 adults with long-standing depression, two doses of psilocybin given with supportive psychotherapy produced effects that were still holding at twelve months, with 75 percent response and 58 percent remission. Small study, controlled research setting, substantial clinical support. But real.
Note the second half of that description. The medicine was given with preparation and support. The opening is not the treatment. What gets built during it, through integration and the work that follows, is what lasts.
And the same medicines can be unhelpful or harmful for someone whose system is already struggling to hold coherence. This is why careful screening exists in psychedelic therapy, and it's worth saying plainly that this is standard clinical practice rather than an inference from the criticality model. Active psychosis, severe dissociation, and acute crisis are exclusions for good reason. A person in those states needs coherence, structure, and containment, and a medicine that increases entropy pushes the wrong direction.
What Happens Near the Edge
When the brain is operating in that workable range between rigidity and randomness, something specific becomes possible.
Insight happens here. The moment a new pattern emerges from a previously unsolvable problem. The flash of seeing something clearly that had been opaque. The sudden recognition of a connection that had been invisible. These are the experiential signatures of a system structured enough to integrate and flexible enough to discover.
This is part of why psychotherapy at depth so often involves sudden moments of clarity rather than gradual accumulation. The work, in some sense, is bringing the system to a state where new pattern-recognition becomes possible. The insight emerges from that condition, not from accumulated effort alone.
The change happens not because new information has arrived, but because the system's capacity to reorganize has been temporarily restored.
Why the Work Is About Balance, Not Fixing
This framework has changed how I think about the work, and I want to share that shift.
The traditional medical model approaches mental health by identifying a disorder and applying a treatment to fix it. Find the symptom. Match it to an intervention. Reduce the symptom. Move on.
The criticality framework suggests something different. The goal isn't to fix a broken system. It's to help a system that has drifted too far from its working range find its way back.
Depression isn't a deficit. It's a state of excessive order.
Anxiety isn't a flaw. It's usually excessive order too, running on threat rather than on hopelessness.
Trauma isn't damage. It's a system that locked into protective patterns and lost some of its capacity for flexibility.
Different drifts call for different tools. A system that has drifted toward too much order may benefit from interventions that introduce some healthy disorder: new experiences, deeper emotional work, movement, expanded perspective, and in some cases psychedelic therapy. A system struggling to hold coherence may benefit from interventions that restore structure: grounding, routine, body-based regulation, nervous system stabilization, and the steady containment of a therapeutic relationship.
Most people need both, in sequence. Even someone whose core problem is rigidity usually needs enough stability in place first to tolerate the loosening. That ordering matters more than it gets credit for. Loosening a system that has nothing to hold it is not treatment.
A Few Implications
If this framework lands for you, some things worth holding.
Suffering as drift rather than defect. Drifts can be corrected. A system that learned to over-order can relearn flexibility. A system that fragments under stress can relearn coherence.
Healing is often about restoring range, not removing something. You aren't broken. You're off-center, in a direction that can be named.
Knowing your direction matters. Whether a pattern sits on the order side or the coherence side changes what will help. The anxiety example is the useful one here, because the obvious read and the accurate read point to different interventions.
Psychedelics are a specific tool for a specific problem. Useful for excessive order, risky for compromised coherence. Assessing which one you're dealing with is a substantial part of what careful psychedelic-assisted therapy involves.
Insight lives near the edge. Much of the work is the slow business of bringing a system to a state where reorganization becomes possible, and then supporting whatever emerges.
A Closing Thought
The brain is the most complex object we know of. That it manages, most of the time, to hold itself in a state where consciousness can emerge, where flexible thought and emotional life and the felt sense of being you all become possible, is itself remarkable.
When that balance is lost, suffering follows. The kinds of suffering that bring people to therapy are not random. They're the predictable patterns that emerge when a complex system has drifted from its working range.
The work of healing, at its deepest, is helping the system find its way back. Not to some idealized state. Just back to the balance that lets life feel like life again. Coherent enough to make sense, flexible enough to surprise you, alive enough to matter.
That's what I think good therapeutic work is actually doing. Not fixing broken machines. Helping living systems remember how to live near the edge, which is where most of what matters about being a conscious creature happens.
You Are a Controlled Hallucination: What This Means for Suffering and Healing
Neuroscientist Anil Seth argues that consciousness isn't passive reception of reality — it's an active, ongoing construction your brain produces moment by moment, including your sense of being a self. A therapist on what this framework reveals about trauma, depression, psychedelic therapy, and why understanding yourself as a process rather than a fixed thing opens up new possibilities for healing.
There's a quiet revolution happening in the science of consciousness, and most people haven't heard about it.
For centuries, we've assumed that perception works in a particular way. You open your eyes, light hits your retina, your brain receives that information, and you see the world. The brain is essentially a camera, recording what's out there.
This picture is wrong. Or at least, deeply incomplete.
Something stranger and more interesting is emerging from cognitive neuroscience. The neuroscientist Anil Seth lays it out in his book Being You: A New Science of Consciousness. Your brain doesn't receive reality. It predicts reality, then uses your senses to correct its predictions. Most of what you experience as the world out there is actually a model your brain is generating, moment to moment, and adjusting based on sensory input.
Seth calls this controlled hallucination. The phrase sounds provocative, but it's surprisingly accurate. Hallucination, because the brain is generating the experience. Controlled, because the generation is constrained by what your senses are picking up from the world.
This idea matters far beyond consciousness research. It changes how we understand suffering, healing, trauma, and what psychedelic experiences are actually doing to the brain. I want to walk through why. Once you understand the framework, a lot of what happens in psychological work becomes clearer, and especially what happens in psychedelic-assisted therapy.
The Brain as Prediction Engine
The traditional model of perception was passive. Information comes in, the brain processes it, you experience the result.
The newer model works the other way. It's sometimes called predictive processing. Your brain is constantly generating predictions about what should be happening, then comparing those predictions to incoming sensory information. When the prediction matches reality, the experience feels seamless. When the prediction misses, your brain updates.
This sounds technical, but you can feel it in everyday life.
When you're walking down a familiar staircase and you miscount the steps, you get that brief lurching feeling. Your foot goes farther than expected. Your balance unsettles for a moment. That's your brain's prediction error becoming briefly visible. You expected solid ground. Sensation didn't deliver it. The mismatch produced the strange falling sensation.
When you read a sentence with a missing word, your brain often fills in the word automatically. The prediction is so confident that the absence doesn't even register at first. Magicians and optical illusions work by exploiting predictable predictions and producing experiences that contradict them.
Your everyday experience of the world, its colors and solidity and continuity, is largely your brain's confident model of what should be there, lightly corrected by what your senses actually report. Most of the time, the model is so accurate that you experience the world directly. But the experiencing is happening one layer in from reality.
What This Has to Do With You
Here's where Seth's framework gets personal.
If perception of the world is a controlled hallucination, so is your perception of yourself.
The felt sense of being you is not a thing your brain contains. Your body, your thoughts, your sense of being one continuous person across time. All of it is something your brain constructs, continuously, from sensory signals inside your body, memories, narratives about who you are, predictions about who you'll be, and the constant background processing of what it feels like to be alive.
This sounds destabilizing when stated bluntly. But it's actually how consciousness has always worked. You've never been a static entity inhabiting a body. You've been an ongoing process of self-construction the entire time. The continuity you feel is a kind of beautiful illusion, generated by your brain doing its job.
Seth's framing matters because it points at something useful. If the self is constructed, the construction can change.
The patterns you've been running for years are not features of a fixed self. The harsh self-criticism, the chronic anxiety, the depressive self-narrative, the trauma responses. They're predictions your brain is making, repeatedly, about who you are and what's coming. They've become so confident, so automatic, that they feel like simply who you are.
But predictions can be updated.
Why Trauma Is So Hard to Reach With Words
This framework helps explain something a lot of people struggle to understand about their own healing.
Trauma is, at its core, a prediction your brain made under conditions of overwhelming stress, that then got locked in. The world is dangerous. People are not safe. Closeness ends badly. My body is not okay. These predictions formed in the original moment, often when the system couldn't fully process what was happening. They became default models, the brain's confident assumptions about what to expect.
Years later, the world has changed. The original threat is gone. But the predictions are still running. Your brain is still generating experience based on a model that no longer matches reality, and the sensory information you're getting now isn't strong enough to update the model.
This is why insight alone often fails to change traumatic patterns. You can know, intellectually, that you're safe. The predictive model doesn't care. It was built to be robust against challenge, because at the time it formed, holding it tightly was a matter of survival.
What this framework suggests is that real healing requires more than new information. It requires new experiences strong enough to update the model. Experiences the predictive system can actually feel, in the body, repeatedly, over time. The slow build of new predictions that compete with the old ones until eventually the old ones loosen their grip.
This is what trauma-informed therapy is actually doing, even when therapists don't describe it this way. Not just talking about what happened. Creating new experiences of safety in the body, in the relationship, in the room. Experiences strong enough to begin updating the predictive scaffolding that trauma built.
Where Psychedelics Fit Into This Picture
Here's where Seth's framework connects to psychedelic therapy in a way that's both beautiful and clinically important.
The most influential current model of how psychedelics work is called REBUS, for Relaxed Beliefs Under Psychedelics. Robin Carhart-Harris and Karl Friston proposed it in 2019. It suggests that psilocybin, LSD, and similar compounds work by temporarily loosening the brain's predictive models.
In ordinary consciousness, the predictive system is strong, confident, and stable. The model of self and world it produces feels reliably real because it's been refined over years and is reinforced constantly. Even when the model is causing suffering, it's hard to shift because the brain trusts it so much.
Under psychedelics, this changes. The confidence of the predictions softens. The grip of the model loosens. Sensory information that would normally be ignored or absorbed into the existing model can suddenly be seen freshly. The structures that held the experience of self and world stable become temporarily fluid.
This is why people on psychedelics often describe seeing themselves and the world differently, sometimes radically so. Not because new information has appeared, but because the interpretive scaffolding through which everything was being filtered has temporarily loosened. The model of self can be glimpsed as a model. The story of who you are can be seen as a story.
And this is why psychedelic-assisted therapy may help with trauma, depression, and other patterns of suffering. Not because the medicine fixes anything directly, but because it creates a window in which rigid predictive models can be updated by new experiences. The opening is temporary. What gets built during it, through preparation, support, and integration, is what can become lasting.
Worth saying plainly: REBUS is a proposal, not a settled finding. It's the framework most researchers reach for, and it's elegant, but direct testing of its core psychological claims is still in early stages. I find it useful for thinking with. I wouldn't treat it as established fact.
What it does capture well is why so many practitioners now emphasize that the medicine alone isn't the treatment. The medicine softens the predictive scaffolding. The therapy and integration do the actual updating.
What This Framework Offers
A few implications worth holding.
Your suffering is real, but it's not a fixed feature of who you are. It's a pattern your brain is generating, with reasons. The pattern can change, though changing it usually requires more than insight alone.
The self isn't a thing to be fixed. It's an ongoing process. The work of healing isn't repairing a broken object; it's gradually shifting the patterns of construction. Somatic, relational, contemplative, and psychedelic-assisted work all participate in that shifting.
The body is central. Seth emphasizes that consciousness is deeply tied to interoception, the brain's perception of internal bodily signals. Your sense of being alive, of being you, is grounded in your body's ongoing regulation. This is why body-based work reaches places talk therapy can't. The predictive system that shapes your experience is built from bodily input as much as from anything else.
Psychedelics may have a specific role. Not as fixes, but as catalysts that temporarily loosen the predictive structures so that therapy, integration, and lived experience can produce updates that wouldn't be possible otherwise. That's a more sophisticated picture than either "psychedelics are magic" or "psychedelics are dangerous." They are tools with a proposed mechanism.
Healing is possible at a deeper level than symptom management. If suffering lives in predictive models, the deepest healing is at the level of those models themselves. Not just feeling better, but actually relating to yourself and the world from a different scaffolding. This is what people sometimes mean when they describe profound therapeutic experiences as feeling like they became a different person. The construction shifted.
A Different Way to Understand Yourself
The implication of Seth's work I find most useful, both clinically and personally, is that you have never been the fixed thing you assumed you were.
The self you experience is a continuous act of creation. Your brain, in its remarkable way, is generating you, moment to moment, based on bodily signals and predictions and memories. The version of you that exists now is the latest iteration of a self that has been changing all along, even when it felt static.
This isn't nihilism. It doesn't mean you're not real. It means you're more alive than the old metaphor of a fixed self suggested. You are something happening, not something being. And the something that's happening can move.
Some people have lived inside a particular version of themselves for decades. A depressed self, an anxious self, a self defined by trauma. For them, this framework opens a door. The self that has been suffering is one of many possible selves the brain could be constructing. Different inputs, different practices, different experiences can begin to construct a different one.
This is what the work of healing is, at the deepest level. Not removing something. Building something new, slowly, through repetition, through the body, through relationship, through whatever helps your predictive system update.
A Closing Thought
Anil Seth's framework doesn't solve the deepest mystery of consciousness. He's clear about that. We still don't know, at a fundamental level, why brain activity produces experience at all.
But the framework does something more useful for the question of how to live. It locates suffering and healing in a more accurate place. Not in a fixed self that needs fixing, but in patterns of construction that can change. It connects the work of therapy, somatic practice, psychedelic-assisted experience, and integration into a coherent picture. It suggests that the strangeness of altered states is not strange at all. It's just the ordinary process of self-construction becoming briefly visible.
You are a controlled hallucination. That doesn't make your life less real. It makes it more available than the old picture allowed.
What to Eat Before a Psychedelic Experience: A Practical Guide
What you eat in the hours and days before a psychedelic experience can meaningfully affect how it unfolds — and most of the guidance circulating online is incomplete or inaccurate. A therapist's practical guide to what helps, what doesn't, and why the body's preparation is part of the work itself.
Most of the writing about preparing for a psychedelic experience focuses on mindset and intention. Both matter, and I've written about set and setting at length. But there's a more practical layer that often gets overlooked, and it can meaningfully affect how the experience itself unfolds.
What you eat, and what you don't eat, in the hours and days before a journey shapes your body's response in ways that can either support the experience or quietly create resistance to it. For many people, this is the difference between a session that flows and a session that's interrupted by nausea, discomfort, or digestive distress.
I want to walk through what's actually useful here, because the information that circulates in psychedelic communities ranges from solid to misguided, and the people preparing for an experience deserve clear, grounded guidance.
One note before we start. Most of what follows applies to classic serotonergic psychedelics taken orally. Ketamine works differently and has its own requirements, and I've given it a separate section below.
Why Food Affects the Experience
Psilocybin is a prodrug. Once swallowed, it's rapidly converted to psilocin, and psilocin is the compound that does the work, binding primarily to serotonin receptors including the 5-HT2A receptor.
Serotonin receptors are concentrated in the brain, but a large share of the body's serotonin activity happens in the digestive tract. That's why nausea is one of the most common physical effects. The same signaling that produces the psychological experience also stimulates the gut. Nausea and vomiting specifically are mediated largely through the 5-HT3 receptor, which is the same receptor that anti-nausea medications like ondansetron block. For some people this is mild, a slight queasiness in the first thirty to ninety minutes. For others it can be more intense, occasionally including vomiting, particularly during onset.
The good news is that thoughtful preparation reduces this significantly. Most of the discomfort isn't about the medicine itself. It's about how the medicine interacts with what's already in your digestive system.
In the Days Leading Up
In the three to five days before a session, the goal is to give your body the conditions for clarity and ease.
Eat clean, whole foods. Vegetables, fruits, whole grains, simple protein sources. The kind of meals you'd choose if you were preparing for a physical event you wanted to feel good for.
Stay well hydrated. Adequate water in the days before makes a real difference. Many people are quietly dehydrated even when they think they aren't.
Reduce caffeine and sugar. Both can leave the nervous system more activated, which doesn't pair well with the openness a psychedelic experience asks for. Taper caffeine slowly rather than stopping abruptly, which reduces the risk of withdrawal headaches during the session.
Move your body gently. Light exercise, walks, yoga. Nothing exhausting. The goal is circulation and presence, not depletion.
Avoid heavy or hard-to-digest foods in the 24 hours before. Red meat, fried foods, very rich meals. These take longer to digest and can leave your gut still working when the medicine begins.
Avoid alcohol for at least 24 hours before, ideally longer. Alcohol affects the nervous system in ways that interact unpredictably with psychedelics, and the rebound effects can carry into the next day.
The Medication Conversation
This one deserves its own section rather than a bullet, because it's the item on this list where getting it wrong can actually hurt you.
Talk to a knowledgeable prescriber about everything you take. Some medications, particularly SSRIs and certain mood stabilizers, significantly alter how psychedelics work and may need to be adjusted under medical supervision. This is not a DIY question.
The most serious interaction in this territory involves MAO inhibitors. Ayahuasca contains MAO-inhibiting compounds by design, which is what makes the DMT orally active. Combining MAO inhibition with serotonergic medications such as SSRIs carries a risk of serotonin syndrome, which is a medical emergency. MAO inhibition is also the reason tyramine matters, which I'll come back to below.
If you take any psychiatric medication and you're considering ayahuasca specifically, the medication review isn't optional and it isn't something a retreat intake form can substitute for.
The Day of the Experience
On the day itself, the principle is simple: light, early, and settled.
Eat lightly, well in advance. This is where a lot of circulating advice gets it backwards. Published psilocybin trial protocols generally don't ask participants to fast. They ask for a light, low-fat breakfast taken at least two hours before dosing, and that convention runs across programs at Johns Hopkins, NYU, and Yale. The goal is a digestive system that's mostly settled, not one that's empty.
Don't fast completely unless your provider specifically tells you to. Going in entirely empty produces its own problems: blood sugar drops, weakness, light-headedness. A psilocybin trial in anorexia nervosa documented a case of transient low blood sugar during dosing, which is exactly the scenario complete fasting invites. If you have a history of disordered eating or any condition affecting blood sugar, this is a conversation to have with your provider rather than a guideline to follow from a blog.
Stay hydrated, but don't overdo water immediately before. A full bladder during a multi-hour experience is its own challenge.
Foods That Tend to Help
Potatoes
A surprisingly good choice in the hours before a session. Boiled, baked, or mashed without heavy cream or butter, they're gentle, filling enough to prevent blood sugar drops, easy to digest, and unlikely to leave anything still working in your stomach when the medicine begins. They're also bland enough that they don't compete with the sensory experience.
Plain starches
White rice. Simple pasta. Plain bread or toast. Easy to digest, low in the kind of fiber that might cause distress, and stabilizing for the stomach.
Bananas
Soft, easily digested, and gentle. They also provide potassium and steady carbohydrate energy.
Ginger
If you're prone to nausea, ginger is worth having on hand. Fresh ginger tea sipped slowly in the hour before, or ginger candies during the early part of the experience.
The evidence deserves an honest description. Ginger's active compounds appear to work by blocking the 5-HT3 receptor, which is the same receptor driving psychedelic-related nausea, so the mechanism lines up well. The clinical evidence is strongest for nausea in pregnancy, where a meta-analysis of twelve randomized trials covering more than a thousand women found a significant improvement in nausea compared with placebo, though not in vomiting. For chemotherapy-induced nausea the results are genuinely mixed, with several reviews finding no significant effect. Nobody has studied ginger for psychedelic nausea specifically.
So: plausible mechanism, real evidence in at least one context, low risk, and worth trying. Not a guarantee.
Herbal teas
Peppermint and chamomile in particular. Both are settling for the digestive system and have a long history of use for nausea.
Light broths
If a solid meal feels like too much, a clear vegetable or bone broth can provide some nourishment without burdening digestion.
Foods to Avoid on the Day
Meat and fish. Heavy, slow to digest, and often leave the gut still working when the medicine arrives. Some experienced practitioners recommend avoiding meat entirely for 12 to 24 hours before.
Spicy foods. They activate the gut directly, which is exactly the system you want to keep quiet.
Greasy or fried foods. Slow digestion, and they often produce nausea even on ordinary days.
Very sugary foods. Blood sugar spikes and crashes can amplify the disorientation of the early experience. Avoid candy, pastries, sweetened drinks.
Strong-smelling foods. Garlic, onions, anything you'd notice across a room. Smells get amplified during the experience, and a lingering taste or smell can become unpleasantly prominent.
Aged cheeses, cured meats, fermented foods, if and only if MAO inhibition is involved. These contain tyramine. Normally your body breaks tyramine down without incident. When MAO is inhibited, whether by an ayahuasca brew or by a prescribed MAOI, that breakdown is blocked and tyramine can accumulate, which can cause a dangerous spike in blood pressure. This is a serious and specific interaction, and dietary restriction around ayahuasca is standard for exactly this reason. It does not apply to psilocybin or LSD, which don't inhibit MAO.
Alcohol. Already noted above, but worth repeating. Even small amounts the night before can affect how the experience unfolds.
A Small Practical Note
This one comes up rarely in writing about psychedelic preparation, but it's worth knowing: brush your teeth before the session.
An unpleasant taste in your mouth can subtly amplify nausea, and during a long session you may not realize how much a stale taste is bothering you. Starting clean helps. Some practitioners keep mints or sugar-free gum nearby for the same reason.
During the Experience
Most people don't want food during a psychedelic experience itself. The digestive system has effectively quieted, and the focus is inward.
A few exceptions:
Sips of water. Always available. Take them slowly.
Ginger tea or candies if nausea arises.
Light snacks toward the end. As the experience begins to soften and you're moving back toward ordinary consciousness, a piece of fruit, some crackers, or a small bowl of soup can be grounding. The body often welcomes gentle nourishment as it returns. This is also, quietly, the beginning of integration.
What About Ketamine
Ketamine is the psychedelic medicine that's currently legal in the United States, so for many people reading this it's the relevant one. Almost none of the above transfers directly.
Ketamine isn't a serotonergic psychedelic. It works primarily as an NMDA receptor antagonist, so the 5-HT2A and 5-HT3 mechanisms driving the guidance above don't apply in the same way. The general pharmacokinetic points about digestion and absorption aren't receptor-specific, but they haven't been studied for ketamine either.
What does apply, and applies more strictly, is fasting. Nausea and vomiting are common with ketamine, and vomiting in an altered, reclined state carries real risk. Clinical ketamine protocols therefore specify a fasting window before dosing, and it's typically firmer than anything in the psilocybin guidance above.
I'm deliberately not giving you a number here. The window varies by route of administration, by dose, and by prescriber, and your prescriber's protocol is the one that governs. Ask them directly, get it in writing, and follow theirs over anything you read online, including this. If you want the broader picture of how this work is structured, I've written about what the research shows and about preparation and integration separately.
What Eating Has to Do With the Larger Experience
There's a deeper point underneath all of this practical guidance, and I want to name it briefly.
How you treat your body in the hours and days before a psychedelic experience is itself part of the experience. The care you take in choosing what to eat, the attention to hydration, the small acts of preparation are not separate from the medicine. They are an early form of the intention you're bringing to the work.
People who arrive having paid attention to their bodies often report something subtle but real: a sense of having met themselves halfway. The medicine doesn't have to fight uphill against indigestion, dehydration, or the residue of yesterday's meal. The system is already softening. The body has been told something important is coming, and I am preparing.
A Closing Note
None of this is rigid prescription. People vary. Some have sensitive digestive systems and need more careful preparation. Others can eat normally and feel fine. The guidelines here are a starting point, drawn from clinical protocols and the practical wisdom of practitioners working in this field.
If you're preparing for a psychedelic experience in a legal therapeutic setting, your provider should give you specific guidance, and you should follow theirs over anything in a blog post. If you're preparing for an experience in another context, this may be useful background. And if nausea or difficulty during a session is what you're actually worried about, that's worth reading about directly rather than trying to eat your way around it.
The body is your partner in this work. Treating it with care is part of the work itself.

Psilocybin and Compassion: A New Model for Treating Depression
Psilocybin can loosen the grip of depression in ways little else reaches. What it doesn't reliably touch is the voice inside telling you you're failing. A 2022 paper proposes building the whole treatment inside Compassion Focused Therapy, an approach designed for exactly that voice. It's a proposal rather than a proven treatment, and the question it's asking is the right one.
When people read about psilocybin therapy in the news, the headlines tend to focus on the dramatic part. The mystical states. The breakthroughs. The trials showing rapid relief from depression after years of other treatments not quite working.
The headlines aren't wrong. The experiences can be that profound.
But there's a quieter question underneath, and it gets far less coverage.
What happens after?
Not the week after. The month, the season, the year. When the session has receded into memory and you're back inside your ordinary life with your ordinary mind, what actually carries forward?
What survives the experience
In my clinical work, the thing I watch most closely is the voice.
Someone comes back from a profound session with real insight. Real openness. A felt sense of having touched something that mattered. And then, over weeks, the same critical voice returns. Quieter at first. Then not quieter.
You're falling behind. You're not doing the work right. You should be further along by now. What's wrong with you that you can't make this stick?
That voice is not the depression, exactly. It's something more specific. It's the internalized harshness that many people carry as a kind of baseline. The relentless evaluation of every thought and feeling against a standard that was never reachable. The quiet conviction that something is fundamentally wrong with you.
For a lot of people, that voice isn't sitting on top of the depression. It's closer to the engine. The low mood and the withdrawal and the hopelessness are downstream of an inner relationship that turned adversarial years ago and never turned back.
Which raises an uncomfortable question about psychedelic work. If the medicine opens the system but the relationship inside it stays the same, what exactly has changed?
Someone put this question in writing
In 2022, two clinicians named Wendy Pots and Farid Chakhssi published a paper in Frontiers in Psychology arguing that psilocybin therapy for depression should be built inside a specific framework: Compassion Focused Therapy.
I want to be clear about what kind of paper this is, because it matters and it's easy to misread.
It's a proposal. The authors designed a treatment protocol, explained why they chose this framework over others, and sketched a study that could test it. As of publication, that study hadn't been run. They were still writing the manual for therapists.
So this isn't research showing the combination works. It's a group of experienced clinicians naming a real gap and putting a testable answer on the table. That's worth reading. It's just not the same thing as proof, and anyone presenting it as proof is getting ahead of the evidence.
The gap they name is this. In most psilocybin trials, the therapy wrapped around the dosing session gets described only by its shape. Preparation, session, integration. What actually happens inside those hours often goes unreported. Which leaves the field unable to answer something basic: what is the therapy contributing, and what kind of therapy contributes most?
Why compassion, specifically
Compassion Focused Therapy came out of an observation Paul Gilbert made working with chronically depressed clients who carried a lot of shame and self-criticism.
Those clients could do the cognitive work. They could challenge a thought, complete the worksheet, name the distortion. What they couldn't do was generate a self-compassionate inner voice.
You can correct a thought a thousand times. If the voice delivering the correction is still contemptuous, something essential hasn't moved.
Gilbert's model organizes emotion around three systems.
The threat system. Responds to danger with defense. Anxiety, anger, vigilance. In small doses it keeps you alive. Running constantly, it exhausts you.
The drive system. Achievement, resources, reward. Motivation and striving. In a lot of lives this one is hyperdeveloped.
The soothing system. Safety, connection, care. The capacity to calm and content yourself. This is the one that lets the nervous system actually rest.
In depression, the pattern the paper describes is threat and drive running hot while soothing stays underdeveloped. Sometimes severely. Some people have spent their whole lives without much soothing system activity at all. Driven, watchful, self-critical, and rarely warm with themselves.
Gilbert also uses a phrase I find enormously useful with clients: the tricky brain. The idea is that all of us arrived with an evolved brain and a set of formative circumstances we did not choose, and both of them shaped how we respond. The paper describes this concept as a way to de-shame people. It is not your fault that you have a brain capable of generating these states. It is not your fault that you were born into the circumstances that taught you these patterns.
That reframe alone does something in a room.
Why the authors think these two fit
Their argument is that psilocybin and CFT push in the same direction.
The paper cites research showing psilocybin increases feelings of connection and acceptance, and studies suggesting certain substances can produce increases in self-compassion and reductions in self-criticism similar to what compassion practices produce. People with depression tend to operate from the threat system. Deliver the medicine inside a framework built to activate the soothing system, and you may be doing something the medicine alone doesn't do.
There's evidence the medicine alone does a great deal. In a Johns Hopkins follow-up of 27 adults with long-standing depression, two doses of psilocybin with preparation and support produced large drops in depression that were still holding a year later. The researchers were careful to note this happened in a controlled research setting with substantial support from trained clinicians.
What nobody knows yet is how much of that durability comes from the therapy. The paper says so directly. It remains unclear if and how much therapeutic guidance is necessary. That's the open question at the center of all of this, and I'd rather sit with it honestly than pretend it's settled.
What the protocol actually asks of a person
Thirteen sessions across ten weeks. Two dosing days. Eleven therapy sessions.
That ratio is the part I keep returning to.
The preparation isn't a briefing. It's three sessions of learning the model, learning to breathe in a way that soothes rather than braces, and beginning to work with the different parts of yourself. By the third session you're setting an intention that came out of that work rather than out of nowhere.
The dosing sessions are largely non-directive. You're supported, not steered. The paper describes following the person's lead and trusting their own healing intelligence to determine what surfaces. When parts of the self come up, the therapist can guide you toward meeting them from the compassionate self rather than from the critic.
Then integration, which is most of the protocol. A debrief the day after. Weekly sessions that deepen the compassionate self and put it to work in ordinary life. Compassionate letter writing. Worksheets that address the inner critic directly. Practice, and more practice, and a final session that reviews what you've built and plans for the days it slips.
Two days of medicine. Eleven sessions of learning how to speak to yourself differently.
What's still open
The authors are candid, and I'd rather repeat their caution than smooth over it.
They don't know how much therapy is necessary. They also say plainly that other frameworks might work as well. Acceptance and Commitment Therapy has been proposed for the same purpose. CBT and Motivational Enhancement Therapy have been paired with psilocybin for other conditions. Their case for CFT is that it targets compassion and connection specifically, which may suit people high in shame and self-criticism. That's a reasonable hypothesis. Nobody has run the comparison.
Two more limits worth naming. The protocol was built for depression and the authors don't recommend generalizing it elsewhere. And it isn't meant for use with other psychedelics or medications.
The deeper shift
What stays with me here isn't a treatment recommendation. It's a change in what treatment is for.
Most mental health care is organized around symptom reduction. The score comes down. The subscale improves. Those things matter and I don't want to be glib about them.
This model is pointing at something else. It asks whether your default response to your own suffering is judgment or care, and treats that as the thing to change.
Many people have never really had the second one. They've been their own harshest critic so long that the harshness doesn't register as separate from who they are. It just feels like accuracy.
Whether psilocybin plus CFT turns out to be the best route there, I don't know. Neither does anyone else yet. But the premise underneath it holds regardless of how the trials come out: the relationship you have with yourself is not a fixed feature of who you are. It can be worked with directly. It can change.
For someone who has spent decades inside a punishing inner relationship, that possibility can be one of the more significant things they encounter.
Psilocybin may help open the door. The slow, unglamorous work of building self-compassion is what makes the room livable.
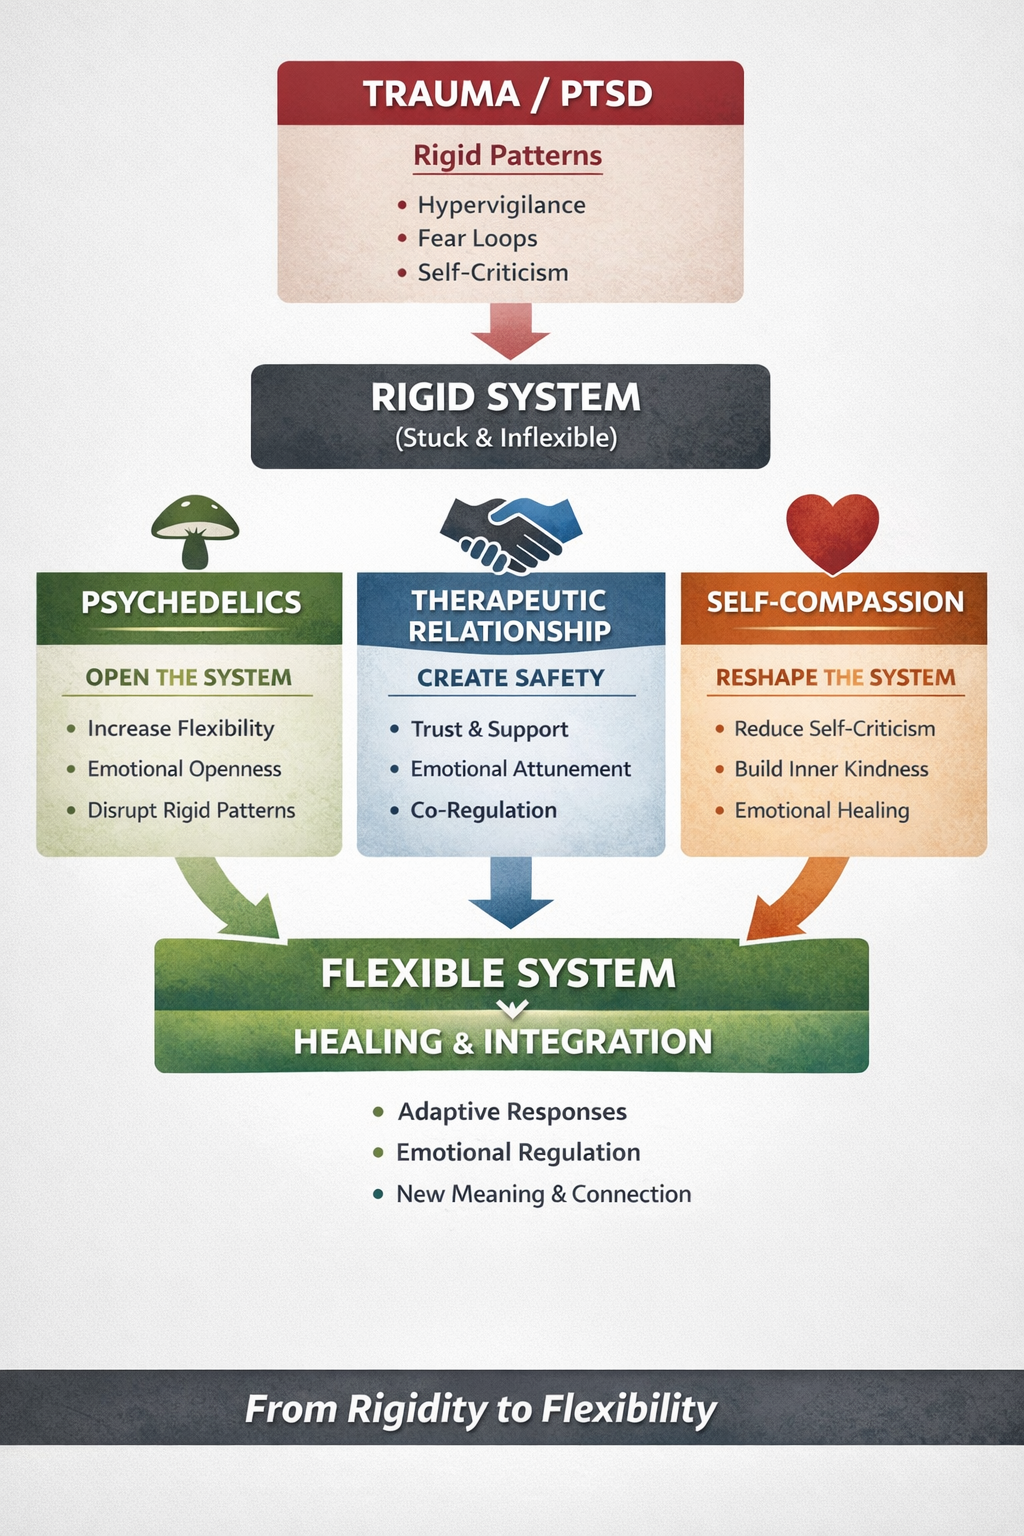
How Healing Actually Works: Psychedelics, Compassion, and the Power of Relationship
A 2023 study followed 86 Special Operations Forces veterans through a psychedelic treatment program and found significant reductions in PTSD and alcohol misuse — but the deeper finding wasn't really about the medicines. A therapist on what the veterans' experience reveals about how healing actually works, and why no single intervention is ever enough on its own.
There's a particular kind of suffering that doesn't always respond to the treatments we have.
The combat veteran with PTSD who has tried multiple medications, several courses of therapy, and is still waking up at three in the morning unable to settle. The first responder whose nervous system hasn't been able to stand down for years. The person whose trauma is so old and so layered that ordinary treatment can reach part of it, but not the part that's actually keeping them locked in.
These are the people who teach us, when we listen, that healing is more complicated than our standard models suggest. And in 2023, a study published in Military Psychology added something important to what we know about what's possible for people in this kind of suffering.
The study followed 86 U.S. Special Operations Forces veterans: Navy SEALs, Special Forces, and Special Operators. These men and women traveled to Mexico for a single psychedelic treatment program involving two compounds: ibogaine and 5-MeO-DMT. These were not casually exposed individuals. They were combat veterans with significant trauma exposure, many with co-occurring alcohol misuse and post-traumatic stress symptoms.
What the researchers found was striking. One month after treatment, participants reported substantial reductions in PTSD symptoms, depression, anxiety, and problematic alcohol use. Many described the experience as among the most meaningful of their lives.
But the deeper finding, the one I want to spend time with, wasn't really about the medicines. It was about what the medicines opened, and what made that opening usable.
What This Study Actually Showed
The combination of ibogaine and 5-MeO-DMT, paired with preparation and integration support, appeared to produce something traditional treatment for these veterans had often not been able to reach.
Why this matters: veterans with combat-related PTSD are notoriously difficult to treat. Standard protocols like cognitive processing therapy, prolonged exposure, SSRIs, help some. But a significant percentage of veterans remain symptomatic after years of treatment. For this population, the combination of psychedelics and structured therapeutic support seemed to reach something the other tools couldn't.
The researchers were careful not to overstate what they had found. This was an observational study, not a randomized controlled trial. The veterans self-selected into treatment, which introduces bias. The follow-up period was short. But within those limits, the findings pointed toward something worth taking seriously: a different model of healing might be possible for the people standard treatment has been failing.
That different model is what I want to talk about, because it's not just about veterans, and it's not just about ibogaine. It's about what the research is increasingly suggesting about how change actually happens in people whose suffering has stayed stuck.
Trauma as a System That Stopped Updating
To understand why this kind of treatment may work where others haven't, it helps to look at what trauma actually is at the system level.
Trauma is not, fundamentally, an event. It's a pattern that won't update. Something happens that the nervous system can't fully process in the moment. To survive, the system adapts. It learns vigilance. It learns to brace. It learns to suppress what can't be felt. It learns to expect the next threat.
These adaptations are intelligent. They saved your life, or made an unbearable situation bearable. The problem is that they don't shut off. The nervous system that learned to scan for danger in 2007 is still scanning in 2026. The body that braced against grief in childhood is still braced today. The system has become rigid, locked into a configuration that no longer matches the world the person is actually in.
The challenge of healing trauma isn't really about removing the memory or correcting the thought. It's about helping a system that has become rigid become flexible again.
This is where psychedelics enter the picture. Not as cures. As something more interesting: as catalysts that can temporarily soften the structures the trauma is held in, creating an opening for the system to reorganize.
What Psychedelics Actually Do at the System Level
The neuroscience suggests that psychedelic medicines like psilocybin, ibogaine, MDMA, and 5-MeO-DMT share a common effect, though they work through different mechanisms: they temporarily increase the brain's flexibility, sometimes called neural plasticity or cognitive flexibility.
What this looks like, in lived terms:
Rigid thought patterns soften. Defenses ease. The grip of old narratives loosens.
Material that has been carefully kept at a distance can come into view. Emotions that have been frozen can move. Memories can be revisited with something other than the original terror.
This is the opening. And for many people, including the veterans in the study, the opening itself is meaningful. The sense of being released, even briefly, from a pattern that has felt like a permanent feature of one's life can be one of the most significant experiences a person ever has.
But here's the part the research keeps confirming, and the part most marketing of these medicines glosses over:
The opening, by itself, is not the healing.
If the system opens and there is no structure around it, no relationship to hold what surfaces, no support to integrate what emerges, the opening tends to close again. The pattern reasserts itself. The relief proves temporary. People often describe this as the worst version: glimpsing freedom and then losing it.
What turns the opening into actual healing is what surrounds it.
What the Veterans' Experience Reveals
The Special Operations Forces veterans in the Armstrong study didn't just take ibogaine and 5-MeO-DMT and go home. They were in a structured program with preparation, supervision, and integration support. The researchers identified specific elements of the experience that participants associated with their improvement
Three things kept showing up:
The experience itself. The altered state, the encounters with memories and emotions and material that had been stored away, the felt sense of being released from rigid patterns. The medicine produced something that traditional therapy hadn't been able to deliver: a direct, embodied experience of being outside the trauma pattern, even temporarily.
The relational container. The veterans were not alone. They were in a setting with people who knew what to do, who had presence and skill, who created the safety required for the opening to be workable rather than overwhelming. The participants consistently named the importance of feeling supported and held.
Integration. What happened after the experience mattered as much as what happened during it. The work of metabolizing what came up, of bringing insights into ordinary life, of letting the system reorganize around what had been revealed.
The medicines were one of three legs of the stool. Without the other two, the relationship and the integration, the medicines alone would not have produced what they produced.
The Inner Layer: Self-Compassion
There's a fourth piece that the research, and my clinical experience, keep pointing toward.
It's not enough to soften the trauma pattern, provide a safe container, and integrate the experience. For lasting change, the internal relationship — the one between the person and their own suffering — has to shift too.
For people with long trauma histories, the inner relationship is often punishing. Harsh self-criticism. Persistent shame. The conviction that something is wrong with them at a fundamental level. These patterns survive even profound psychedelic experiences. They reassert themselves in the weeks and months after, often quietly undoing what the experience opened.
Self-compassion, by contrast, creates a different kind of inner ground. Instead of meeting the difficult material with judgment, the person learns to meet it with care. The research is now clear that this isn't soft thinking, it's a measurable shift in nervous system regulation, in emotional resilience, and in capacity to integrate difficult experience. It changes how pain is held, even when pain remains.
Many of the veterans in studies like this one have described, in their own words, something like this: they discovered they could meet their own history with something other than the harshness they had been carrying for years. That shift in inner relationship, more than any single insight, was what allowed the changes to take root.
A Unified Picture
Looking across the trauma research, the psychedelic research, the work on therapeutic relationship, and the work on self-compassion, a unified picture emerges that I find clinically and personally meaningful.
Healing isn't really one thing. It's the interaction of several things, all of which have to be present for real change to happen:
Opening — through medicine, through movement, through experience, through any of the practices that temporarily loosen the structures that suffering has been held in.
Holding — through relationships of real safety and skill, both with practitioners and with people who can witness what's emerging without flinching.
Integration — through the slow work of letting what was opened become woven into ordinary life, the patterns of behavior, the body, the choices, the way time gets spent.
Inner softening — through the slow change in how a person relates to themselves, from criticism toward care.
When all four are present, lasting change becomes possible. When any of them is missing, the work tends to stall.
What This Means Beyond Veterans
The Armstrong study focused on veterans, but the model it points to applies more broadly. Anyone whose suffering has stayed stuck despite their best efforts — through trauma, through chronic depression, through anxiety that hasn't responded to standard treatment, through addiction patterns that won't release — may benefit from understanding healing this way.
Not as a single intervention to find.
But as a system of openings, holdings, integrations, and inner shifts, all of which have to come into alignment.
Psilocybin therapy, when it becomes legally available, will offer one path. Ketamine-assisted psychotherapy is already offering another. Plant medicines in legal jurisdictions offer others. Even without medicines, the same model applies: openings can come from breathwork, from somatic practice, from deep contemplative work, from moments of grace. What matters is that the rest of the structure be in place to hold and integrate what opens.
A Closing Reflection
What I find most moving about the Armstrong study, and about the broader research it joins, is what it implies about the nature of suffering.
The suffering of these veterans was not a personal failing. It was not a moral weakness. It was a nervous system that had organized itself around survival under conditions most of us will never face, and then could not, on its own, find its way back to flexibility.
What helped them wasn't a single intervention. It was a coordinated process: the medicine that softened the structure, the relationship that held the opening, the integration that let the change take root, the slow shift in how they met themselves afterward.
This is, I believe, how healing actually works. For veterans, for survivors of childhood trauma, for anyone whose suffering has stayed locked in a system that stopped updating.
Healing happens when rigid systems become flexible again; through openness, safety, integration, and the slow turning of compassion inward. None of these alone is enough. Together, they make change possible that none of them could produce on its own.
If you're sitting with what feels like a pattern that won't update, and you'd like to explore what this kind of integrative work could look like for you, you're welcome to book a consultation.